product

Understanding Stability of Injectable Products
Quality assurance in pharmaceuticals hinges on stability. For injectable products, where safety, potency, and sterility converge, stability is not just a matter of convenience; it is a scientific and regulatory requirement. Stability determines how the product’s shelf life is established, how recommended storage conditions are ascertained, container-closure compatibility, labelling, and most importantly, patient safety.

This article discusses the fundamentals of stability for injectable products, the design and implementation of stability programs, and the analytical and microbiological considerations separating the different injectable types: small molecules, biologics, and lyophilized products.


What Stability Means for Injectable Products

With an injectable formulation, stability means the product will retain its intended physical, chemical, microbiological, therapeutic, and toxicological limitations and characteristics until its expiry date. Stability incorporates several connected subdomains:

Chemical stability — the active ingredient has to retain its potency and purity and not produce dangerous degradants.

Physical stability — clarity, color, and viscosity must be maintained. Precipitation, crystallization, and phase separation must be avoided.

Microbiological stability — for microbiologically sterile preparations, sterility must be maintained. For multi-dose containers, preservative efficacy must be retained.

Particulate stability — no particulate matter, whether visible or sub-visible, must form over time.

Container-closure compatibility — the product and its packaging must not interact significantly through leaching or adsorption.

These aspects collectively determine a product’s shelf life, storage conditions, and in-use stability.


Why Injectables Require Special Stability Attention

Injectables go directly into the body’s sterile spaces, like tissues and blood. Any product instability could have immediate and serious consequences.

Toxic Degradants. Degradation products, even in small amounts, can be toxic.

Sterility Maintenance. Loss of preservative activity can lead to the introduction and growth of germs and subsequent infections.

Physical Changes. Precipitation and other physical changes can lead to the formation of emboli and inflammation.

Biological Sensitivity. Structural fragility of proteins and peptides can lead to denaturation through heat, light, and mechanical stress.

Consequently, injectables warrant more detailed data and continuous monitoring, tighter specs, and more comprehensive oversight compared to other forms like tablets and capsules.


The Regulatory Framework for Injectable Stability

All injectable stability programs must adhere to internationally harmonized standards and guidelines. The key authorities defining the principles and requirements for stability programs include the:

International Council for Harmonisation (ICH) — with guidelines Q1A(R2) and Q1B on the design, conditions, and photostability of stability studies.

World Health Organization (WHO) — stability testing guidance for APIs and finished products in diverse climates.

U.S. Food and Drug Administration (FDA) — comprehensive design, testing, and documentation expectations for stability programs.

UK Medicines and Healthcare products Regulatory Agency (MHRA) — the incorporation of ICH guidelines into the UK framework.

Pharmaceutical Inspection co-operation Scheme (PIC/S) — embedding stability expectations in the Good Manufacturing Practice (GMP) standards for inspection and compliance.

All together, these frameworks establish and control the global standards for assessing stability of injectable products.


Designing a Stability Program for Injectables

For a good stability program, you must have these key parts:

a. Stability-Indicating Analytical Methods

Tests must be proven to show when a product breaks down. Tools like HPLC or UPLC help to split and count the main drug parts and the breakdown products. Other tests, such as looking at pH, how thick a mix is, and checking for tiny bits, add to the chemical checks.

b. Stress Testing / Forced Degradation

Using high stress (like heat, light, adding oxygen, or extreme pH levels) helps find out how and why a product may break down. This also makes sure that the tests used can truly show if a product does remain stable.

c. Selection of Storage Conditions

Picking the right long-term, middle, and fast storage needs is key. Most of the time, long-term settings are 25°C/60% RH or 30°C/65% RH, based on weather zones. For cold items, a range of 2–8°C is normal. For things like shots, how they react to light and heat matters a lot.

d. Batch Selection

Often, tests are run on at least three large-scale batches that show what the making step is like. For things made from living systems, more checks might be needed due to how much they can change.

e. Container-Closure Compatibility

The pack set-up needs to be checked for any parts that might get out, bind, or stick to the drug bits. How they work with glass, plastic, rubber tops, or silicone oil in ready-to-use shots must be looked at with care.

f. Microbiological and Particulate Control

Tests need to show that the product stays clean and the preservatives work. For vials used more than once, the stability after many uses must be checked.

g. Photostability

A lot of injections break down when hit by light. So, these products are put under certain light levels and types to see if they need special packaging or labels.

h. In-use or Dilution Stability

When a product is mixed with other fluids before use, studies have to prove that it stays stable and works well with the tools used to give it.

Special Considerations: Small Molecules, Biologics, and Lyophilisates

a. Small-Molecule Injectables

These are often more firm in their makeup but may face issues like breaking down, reacting with oxygen, or light damage. Efforts on maintaining their stability focus on watching over their purity, acidity levels, and any tiny particles.

b. Biologics (Proteins, Peptides, Vaccines)

These products are very open to harm from their surroundings. They can change shape, stick together, or lose their power even in gentle settings. Hence, tests focused on clumping (with methods like SEC, DLS), checking strength, and maintaining structure are very important. Freeze-drying is a common method used to keep them stable.

c. Lyophilized (Freeze-Dried) Products

For freeze-dried injectables, assessing both the dried form and the mixed solution is crucial. Things like left-over moisture, how quick they mix, and how they hold up after mixing are vital. How well they are packaged is also very important to keep them stable over time.

Particulate Matter: A Critical Quality Attribute

Small bits in items can be a big risk to people. Tests to check how long the product lasts should watch for both big and tiny bits.

  • Visible Particles — If you can see the bits with your eyes, the batch is no good.
  • Sub-visible Particles — Measured by how they block light or how they move in a flow. There are set rules for bits larger than 10 µm and 25 µm in drug standards.

For shots that go in your body made from proteins, clumps of protein can look like bits and might start body defenses by mistake. Because of this, high-level tests are used to tell apart bits from outside and inside.

Bracketing and Matrixing in Stability Studies

Bracketing and matrixing are ways to test efficiently while still keeping data good.

  • Bracketing is when you test only the most and least strong settings (like highest and lowest doses, biggest and smallest boxes).
  • Matrixing is when you test just a few examples at each time.

Both ways need a good reason behind them and must be used with care for risks.


Ongoing Stability and Post-Approval Commitments

Stability checks do not stop when a product gets the okay. Makers have to keep doing ongoing stability studies on what they make, all through the product’s live time.

These checks make sure that the way they make things is still good and that the product stays up to its set quality as time goes by.

If there are any changes after approval — like new suppliers, places where they make things, or what they wrap products in — they need extra stability studies to show things are still alike.


Temperature Excursions and Cold Chain Management

For many shots, like biologics and vaccines, keeping the right temp during storage and moving them is key. Programs to keep them stable must have:

  • Studies to set clear temperature excursion limits.
  • Checking freeze–thaw cycles to see how tough the product is.
  • Writing down rules for cold chain management, including checked wraps and ways to move stuff.
  • Labelling instructions that tell the do’s and don’ts for temp limits (for example, “Do not freeze” or “Use within X hours after taking out from cold storage”).

Info on how these items are handled and moved in real life should help with what the labels say.


Analytical Techniques Commonly Used in Stability Studies

A strong stability program needs good tools that can spot both chemical and physical changes. Often used methods are:

  • HPLC/UPLC — for testing and breaking down products.
  • Mass spectrometry — for making sure of the structure and finding how things break down.
  • Size exclusion chromatography (SEC) — for checking the gathering of proteins.
  • Dynamic light scattering (DLS) — for measuring how big particles are.
  • Microbiological assays — for checking if things are sterile, if there are toxins, and if preservative works.
  • Rheological analysis — for checking how thick things are and if they stay the same physically.
  • Extractable and leachable studies — using tools like GC, LC-MS, and ICP-MS to test for harmful substances.

All these methods must be checked for their aim, how sensitive they are, and if they can be done again, making sure they truly show stability.


Risk-Based Approach in Stability Studies

Risk-based ideas are now a big part of making plans for stability. By checking risks, you can focus on key parts, cut down on tests you don’t need, and still stick to the rules.

Key things to think about:

  1. What traits are key for safety and how well the product works?
  2. What breaks down most often?
  3. How do changes in making or packing touch stability?
  4. What could go wrong with the environs during keeping and moving?

Make sure to write down risks and reasons in the stability plans and reports.

Key Expectations from Regulatory Agencies

Regulators want stability plans for injectables to show:

  1. Use of tested, sure methods that can show stability.
  2. Proof of stress tests to know how they break down.
  3. Test batches that show all mixes and pack types.
  4. Meet rules for test conditions (long-term, middle, fast).
  5. Data on stability under light for light-sensitive items.
  6. Proof of how well it fights germs and keeps preservatives working.
  7. Tests for how the container reacts with the content and checking for chemicals leaking.
  8. Keep a steady, ongoing program with info ready for checks.
  9. Check the risks for any grouping or mixing methods.

Common Stability Pitfalls and How to Avoid Them

  1. Non-Stability-Indicating Methods — Methods that can’t split up degradants fail to see when things start to break down.
  2. Ignoring Physical Instability — Biological products might clump together without showing chemical changes.
  3. Inadequate Container Interaction Studies — Not checking early for leachables or sticking can lead to product recalls.
  4. Weak In-use Data — Bottles used many times must prove that their protecting stuff works after each use.
  5. Neglecting Temperature Excursion Studies — Skipping these tests can cause trouble during real-life shipping, making products unusable.

Taking care of these issues early helps in easier reviews and makes sure products are safe.

Integrating Science with GMP

Getting the steadiness right for injectables isn’t just a lab job—it’s a mix of strict science and sticking to GMP rules. Tests need to match up with checked making steps, strong paper work, and data systems you can track.

GMP check groups want makers to keep easy-to-find, full, and traceable steadiness data. If things don’t go as planned or the results are off, you need to look into it and write down what you will do to fix it.

For complex or new injectables, it’s smart to talk to rules setters early. This helps make sure you meet their needs and skips the need for doing the work again, which can cost a lot.


The Stability of Injectable Products

The keeping of injectable items steady is a mix of chemistry, tiny life study, pack tech, and rule following. A strong steady plan makes sure the item works as it should, stays safe, and keeps its power all through its life.

Key Aspects:

  • Injectable items, as they are high-risk mixes, need a careful way to look at, test checking, and ongoing watch.
  • Global rules from groups like ICH, WHO, FDA, MHRA, and PIC/S make sure there is a steady science and rule plan all over the world.

In the end, keeping things steady is not just about the tech needs but also about staying true to the safety of the patients and trust in the item. This trust is what makes the base for belief in injectable drugs.

Understanding Stability of Injectable Products Read More »

How Do Pharmaceutical Companies Make Money?

Pharmaceutical companies make money by discovering, developing, and commercializing medicines that address unmet medical needs. Their core business model is built around patented prescription drugs, but revenue also comes from vaccines, over-the-counter products, licensing, partnerships, and services. Below is a clear, up-to-date breakdown of where the money comes from, how prices are set, what patents really do, and the key risks and trends shaping pharma profits.


Who actually pays for medicines?

  • United States: A mix of commercial insurers, Medicare/Medicaid, pharmacy benefit managers (PBMs), employers, and patients (copays/coinsurance). PBMs negotiate rebates from manufacturers.
  • Europe and many other countries: Central or regional health systems negotiate prices, often with health technology assessment (HTA) bodies (e.g., NICE in the UK).
  • Low- and middle-income countries: Government tenders, international organizations, and differential pricing strategies often apply.


The core engine: Patented prescription drugs

  • Innovation drives value: Most revenue comes from branded drugs protected by patents/data exclusivity. These drugs command higher prices due to novelty, clinical benefit, and lack of direct competition.
  • Specialty focus: Over the past decade, growth has shifted toward specialty and rare-disease therapies (oncology, immunology, gene/cell therapy), which often serve smaller populations at higher per-patient prices.
  • Blockbusters: A small number of products can contribute a disproportionate share of total revenue and profits.


Mindfulness and Meditation Techniques

How pricing works (and why “list price” isn’t what it seems)

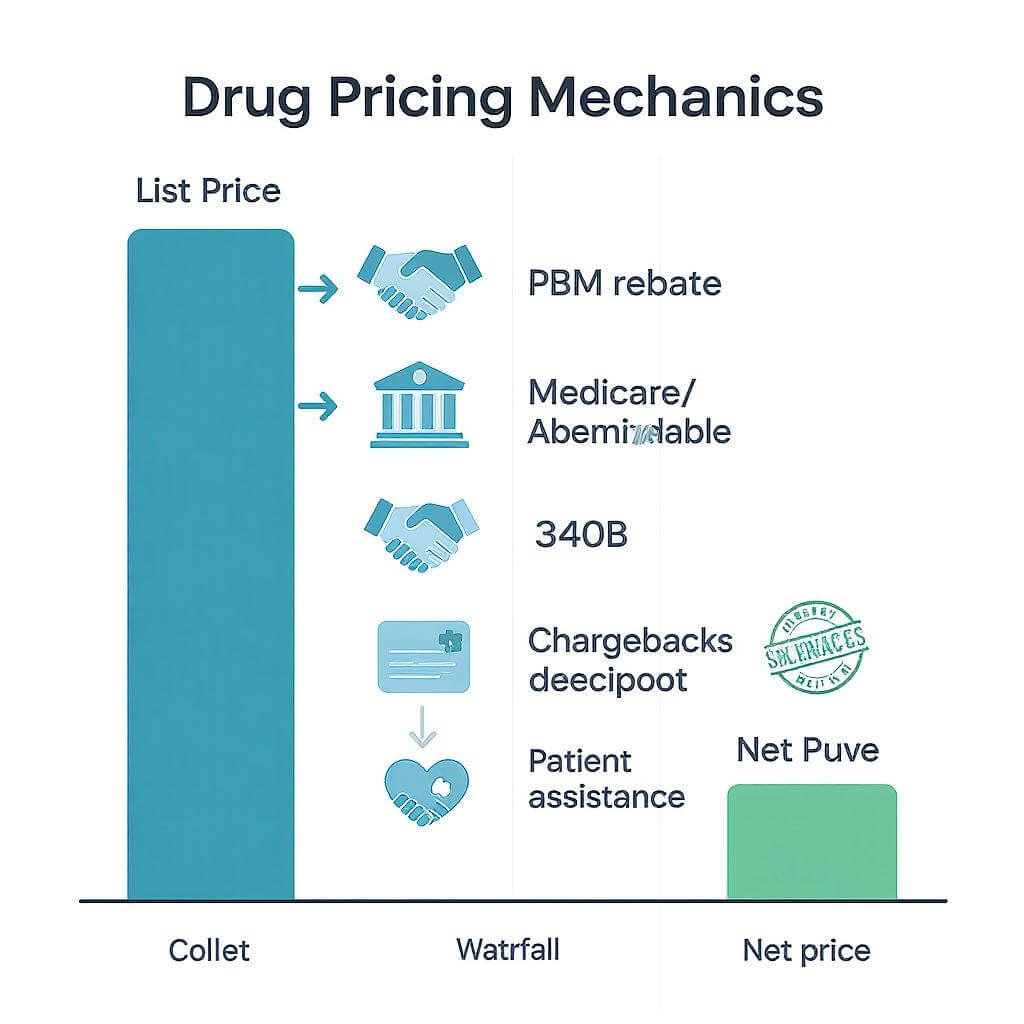
  • List price vs. net price: In the U.S., manufacturers set a list price (WAC), but pay mandatory and negotiated discounts: rebates to PBMs/insurers, government discounts (Medicaid, 340B), chargebacks, and patient support. Net price = list price minus all these concessions.
  • The “gross-to-net” gap: For many branded drugs in the U.S., net price can be 30–60% below list price, depending on the product and payer mix.
  • Outside the U.S.: Prices are usually negotiated nationally, subject to reference pricing and value assessments, often resulting in lower net prices than in the U.S.

Patents and exclusivity protect profits (for a time)

  • Patents: Typically last 20 years from filing. Because filing often occurs early in development, effective post-approval exclusivity is often 7–12 years.
  • Regulatory exclusivity (U.S.): New Chemical Entity (5 years), biologics (12 years), orphan drugs (7 years), pediatric exclusivity (6 months), plus various add-ons. EU uses “8+2+1” data/market protection.
  • Lifecycle management: Companies extend value via new indications, pediatric studies, new formulations (e.g., extended release), device-drug combos, and authorized generics.

The R&D pipeline economics

  • High risk, high cost: Only a minority of candidates that enter human trials achieve approval. Industry-wide, roughly 1 in 10 (varies by therapy area) successfully reach market.
  • Timelines: Discovery and preclinical can take 3–6 years; clinical development and review often add 6–10 years.
  • Investment scale: Total cost to develop an approved medicine varies widely (hundreds of millions to several billions of dollars, depending on modality and failure-adjusted costs).
  • Portfolio logic: A few big winners often offset many failures—one reason companies value platforms and scalable science (e.g., mRNA, antibodies).

Market access, sales, and promotion

  • Access matters as much as science: Formulary placement, prior authorizations, and step therapy affect uptake.
  • PBMs and rebates (U.S.): Manufacturers negotiate rebates for preferred formulary tiers; better placement can drive volume but reduce net price.
  • Promotion: Engagement with healthcare professionals (education, field teams), medical conferences, and—mainly in the U.S. and New Zealand—direct-to-consumer advertising.

After exclusivity: Generics and biosimilars

  • Small-molecule generics: Rapid price erosion and market share loss for the brand when generics launch; margins compress significantly.
  • Biologics and biosimilars: Competition grows more gradually than with pills; price erosion is meaningful but typically slower and less steep than small molecules.
  • Authorized generics: The brand company may sell a “generic” version to retain some share as prices fall.

Other revenue streams beyond branded Rx

  • Vaccines: High-volume, tender-driven in many markets; strategic for public health and reputation.
  • Consumer health/OTC: Pain relief, allergy, vitamins, skincare. Some big pharmas have spun these into separate companies, but it remains a revenue category for many.
  • Licensing and royalties: Upfront payments, milestones, and ongoing royalties from out-licensing or co-developing assets and platforms.
  • Collaborations and co-promotion: Shared risk and reward with biotech or other pharmas.
  • Contract manufacturing (CDMO/CMO): Select companies monetize capacity by producing for third parties (more common among specialized manufacturers).
  • Diagnostics and devices: Companion diagnostics can support therapy adoption; some firms bundle device-drug solutions (e.g., auto-injectors).

Regional pricing and market dynamics

  • United States: Higher net prices on average; complex rebates; significant role for PBMs; DTC advertising allowed.
  • Europe: Centralized or HTA-driven price negotiations; outcomes- and value-based agreements are increasingly used.
  • Emerging markets: Volume-driven, tender-based, and differential pricing; growth opportunities with expanding access.

What the P&L often looks like (ranges vary by company and product)

  • Revenue: Volume × net price (after discounts).
  • Cost of goods sold (COGS): Often 5–10% of sales for small-molecule tablets; can be 15–30% for biologics due to complex manufacturing.
  • R&D expense: Frequently 15–25% of sales for large R&D-based companies.
  • SG&A (sales, general, administrative): Often 25–35% of sales, driven by field forces, marketing, and market access activities.
  • Operating margin: Commonly 20–30% for large, diversified companies; varies widely based on mix and lifecycle stage.

Key risks and headwinds

  • Patent cliffs and biosimilar waves
  • Regulatory and price pressures (e.g., U.S. Medicare price negotiations, EU reference pricing)
  • Clinical failures and safety issues
  • Competition from alternative therapies and generics
  • Supply chain and manufacturing complexities (especially for biologics)
  • Litigation and compliance risks

Trends reshaping pharma revenue

  • Biologics, cell and gene therapies: High-value, one-time or infrequent dosing models; experimentation with annuity and outcomes-based payments.
  • Precision medicine: Smaller, biomarker-defined populations with strong clinical differentiation.
  • Real-world evidence and value-based contracts: Tying payment to patient outcomes to support access.
  • AI-enabled R&D: Aiming to improve target discovery, trial design, and success rates.
  • Metabolic and obesity therapies: Rapidly expanding markets influencing payer strategies and budgets.

A quick revenue math example

  • Net revenue = treated patients × duration × net price.
  • Suppose a rare-disease therapy is priced at $300,000 per year, with 2,000 treated patients and an average 15% discount. Net price ≈ $255,000. Annual net revenue ≈ 2,000 × $255,000 = $510 million. From this, the company funds manufacturing, R&D, SG&A, taxes, and profit.

FAQs

Q: How do pharma companies set drug prices?

A: They consider clinical value, unmet need, competitive landscape, target population size, development/manufacturing costs, and payer willingness to reimburse. In many countries, negotiated or value-based frameworks set effective prices.

Q: Why are drug prices often higher in the U.S.?

A: The U.S. relies on market-based negotiations among manufacturers, PBMs, and insurers, with fewer national price controls. Rebates reduce net prices, but patient out-of-pocket can still be high depending on benefit design.

Q: Do pharmaceutical companies profit from generics?

A: Brand-focused companies generally see steep revenue declines when generics arrive. Generic-focused companies earn profits through high-volume, low-margin models. Some brands use authorized generics to retain share.

Q: How long do patents protect a drug?

A: Patents last 20 years from filing, but effective post-approval exclusivity is often 7–12 years due to early filing and development time. Additional regulatory exclusivities can extend protection for specific indications or populations.

Q: What is a PBM and why do rebates matter?

A: Pharmacy Benefit Managers negotiate drug coverage and pricing for insurers/employers. Manufacturers pay rebates for preferred formulary placement. Those rebates lower net prices but can complicate patient out-of-pocket costs.

Q: Why do prices sometimes increase annually?

A: Manufacturers may take list price increases to offset rebates/inflation, support ongoing R&D, or align with market dynamics. However, net prices (after discounts) may rise more modestly or even fall, depending on competition and payer leverage.

Q: How did COVID-19 vaccines generate revenue?

A: Through large government procurement contracts, often at negotiated prices per dose. Economics varied by country, volume, and contract terms; profits were influenced by scale, manufacturing efficiency, and partnerships.

Key takeaways

  • Most pharma revenue comes from patented prescription drugs during a limited exclusivity window.
  • Net price—not list price—drives revenue; U.S. gross-to-net discounts are substantial.
  • R&D is costly and risky; a few winners fund many failures.
  • Profits depend on market access, lifecycle strategy, and geographic mix.
  • Generics/biosimilars reset economics post-exclusivity.
  • Licensing, vaccines, OTC, and services provide diversification.
  • Policy and payer trends (e.g., value-based contracts, price negotiations) are reshaping the model.

How Do Pharmaceutical Companies Make Money? Read More »

Who Sponsors Clinical Trials?

Clinical trials are the backbone of medical advancements, bringing new drugs, devices, and therapies to the market. These meticulously designed studies test the safety and efficacy of medical interventions, paving the way for improved healthcare outcomes. But who foots the bill for these complex and often expensive endeavors? Understanding who sponsors clinical trials provides insight into the intricate ecosystem of medical research and the motivations driving innovation. In this article, we’ll dive deep into the world of clinical trial sponsorship, exploring the key players, their roles, and the impact of their contributions.


What Are Clinical Trials?

Before we explore the sponsors, let’s briefly define what a clinical trial entails. A clinical trial is a research study conducted with human volunteers to evaluate the effects of a medical intervention, such as a new drug, medical device, vaccine, or treatment protocol. These trials are conducted in phases, each with a specific purpose:


Phase I: Tests safety and dosage in a small group.
Phase II: Evaluates efficacy and side effects in a larger group.
Phase III: Confirms effectiveness, monitors side effects, and compares the intervention to existing treatments in large populations.
Phase IV: Post-market studies to gather additional information on long-term effects.

Clinical trials are resource-intensive, requiring significant financial investment, expertise, and time. The costs can range from hundreds of thousands to billions of dollars, depending on the trial’s scope, duration, and complexity. This brings us to the critical question: who sponsors clinical trials, and why?


The Key Sponsors of Clinical Trials

Clinical trials are funded by a variety of entities, each with distinct motivations and goals. The primary sponsors include pharmaceutical and biotechnology companies, government agencies, academic institutions, nonprofit organizations, and, in some cases, individual philanthropists or crowdsourcing efforts. Let’s break down each category.


1. Pharmaceutical and Biotechnology Companies

The pharmaceutical and biotechnology industries are the largest sponsors of clinical trials worldwide. These companies invest heavily in research and development (R&D) to bring new drugs, biologics, and medical devices to market. According to the Pharmaceutical Research and Manufacturers of America (PhRMA), the biopharmaceutical industry spent over $100 billion on R&D in the United States alone in 2022, with a significant portion allocated to clinical trials.


Why Do They Sponsor Clinical Trials?

Profit Motive: Developing a successful drug or device can generate substantial revenue. For example, blockbuster drugs like Humira or Keytruda have earned billions for their manufacturers.
Regulatory Requirements: To gain approval from regulatory bodies like the U.S. Food and Drug Administration (FDA) or the European Medicines Agency (EMA), companies must provide robust clinical trial data demonstrating safety and efficacy.
Market Expansion: Clinical trials allow companies to explore new indications for existing drugs, expanding their market potential.


Challenges and Criticisms

While pharmaceutical companies drive innovation, their sponsorship comes with scrutiny. Critics argue that profit-driven motives may lead to biased trial designs, selective reporting of results, or prioritization of lucrative markets over unmet medical needs. To address these concerns, regulatory agencies enforce strict guidelines, and independent oversight bodies, such as Institutional Review Boards (IRBs), monitor trial conduct.

2. Government Agencies

Government agencies play a significant role in sponsoring clinical trials, particularly for research that may not attract commercial interest. In the United States, the National Institutes of Health (NIH) is a leading sponsor, funding thousands of clinical trials annually. Other agencies, such as the Centers for Disease Control and Prevention (CDC) and the Department of Defense (DoD), also contribute.


Why Do Governments Sponsor Clinical Trials?

Public Health Priorities: Governments fund trials for diseases with significant public health impacts, such as cancer, infectious diseases, or rare disorders.
Noncommercial Research: They support studies that may not be profitable for private companies, such as trials for neglected tropical diseases or preventive interventions.
Emergency Response: During public health crises, like the COVID-19 pandemic, government agencies rapidly mobilize funding for clinical trials to develop vaccines and treatments.

Examples of Government-Sponsored Trials

What Are Clinical Trials and Why Are They Important?


The NIH’s ClinicalTrials.gov database lists thousands of trials funded by federal agencies, covering areas like Alzheimer’s disease, HIV/AIDS, and mental health.
Operation Warp Speed, a U.S. government initiative, provided billions of dollars to accelerate COVID-19 vaccine trials, collaborating with private companies like Pfizer and Moderna.


Advantages and Limitations

Government-funded trials are often seen as impartial, prioritizing patient outcomes over profits. However, their budgets are subject to political and economic fluctuations, which can limit their scope compared to industry-funded trials.


3. Academic and Research Institutions

Universities, medical schools, and research hospitals frequently sponsor clinical trials, often in collaboration with other entities. These institutions are hubs of scientific discovery, conducting trials to advance medical knowledge and improve patient care.
Why Do Academic Institutions Sponsor Clinical Trials?

Scientific Discovery: Academic researchers aim to answer fundamental questions about disease mechanisms, treatment efficacy, or preventive strategies.
Training and Education: Clinical trials provide hands-on experience for medical students, researchers, and clinicians.
Collaboration: Academic institutions often partner with industry or government sponsors, leveraging their expertise and infrastructure.

Funding Sources

Academic institutions typically rely on grants from government agencies, nonprofit organizations, or industry partners. For example, the NIH’s National Cancer Institute funds numerous cancer-related trials conducted at academic medical centers.

Impact of Academic Sponsorship

Academic-sponsored trials often focus on innovative or exploratory research, such as novel therapies for rare diseases or personalized medicine approaches. They also contribute to the training of future scientists and clinicians, ensuring a steady pipeline of expertise in clinical research.

4. Nonprofit Organizations and Foundations

Nonprofit organizations and charitable foundations are vital sponsors of clinical trials, particularly for diseases that receive limited attention from industry or government. Examples include the Bill & Melinda Gates Foundation, the American Cancer Society, and disease-specific groups like the Cystic Fibrosis Foundation.


Why Do Nonprofits Sponsor Clinical Trials?

Mission-Driven Goals: Nonprofits focus on addressing unmet medical needs, such as rare diseases, pediatric conditions, or global health challenges.
Patient Advocacy: Many organizations are founded by patients or their families, driving research to find cures or improve quality of life.
Bridging Gaps: Nonprofits often fund early-stage research or trials that bridge the gap between academic discovery and industry development.


Notable Examples

The Cystic Fibrosis Foundation invested heavily in clinical trials for drugs like Trikafta, transforming the lives of patients with cystic fibrosis.
The Michael J. Fox Foundation funds trials to develop treatments for Parkinson’s disease, including studies on disease-modifying therapies.


Benefits and Challenges

Nonprofit-sponsored trials are highly focused and patient-centered, but their funding is often limited compared to industry or government resources. They may rely on donations, grants, or partnerships to sustain their efforts.

5. Individual Philanthropists and Crowdsourcing

In rare cases, clinical trials are funded by individual philanthropists or crowdsourcing campaigns. Wealthy individuals may donate to specific causes, while grassroots efforts leverage online platforms to raise funds.
Examples

Philanthropy: High-profile donors like Michael Bloomberg have supported clinical research in areas like public health and cancer.
Crowdsourcing: Platforms like GoFundMe have been used to fund small-scale trials or experimental treatments, particularly for rare diseases.


Opportunities and Risks

While these funding sources democratize research, they often lack the scale and rigor of institutional sponsors. Crowdsourced trials may also face ethical concerns, such as inadequate oversight or unrealistic expectations.


Collaborative Sponsorship Models

In many cases, clinical trials are sponsored by a combination of entities working together. For example:

Public-Private Partnerships: Government agencies and pharmaceutical companies collaborate to share costs and expertise, as seen in COVID-19 vaccine development.
Consortia: Multiple stakeholders, including industry, academia, and nonprofits, pool resources to tackle complex diseases like Alzheimer’s or cancer.
Contract Research Organizations (CROs): While not sponsors themselves, CROs are hired by sponsors to manage trial operations, ensuring efficiency and compliance.

These collaborative models maximize resources, reduce duplication, and accelerate the pace of research.


The Role of Patients and Volunteers

While not sponsors in the financial sense, patients and volunteers are essential to clinical trials. Their participation is invaluable, and sponsors often cover costs like travel, medical care, or stipends to ensure accessibility. Patient advocacy groups also influence trial design and funding priorities, ensuring that research aligns with real-world needs.
The Economics of Clinical Trial Sponsorship
The cost of conducting a clinical trial varies widely based on factors like:


Phase: Phase III trials are the most expensive due to large sample sizes and long durations.
Therapeutic Area: Oncology and neurology trials are among the costliest due to complex endpoints and regulatory requirements.
Geography: Trials conducted in multiple countries face higher logistical costs.

According to a 2020 study published in JAMA Internal Medicine, the median cost of a clinical trial is approximately $19 million, with some trials exceeding $1 billion. Sponsors must balance these costs against potential benefits, whether financial, scientific, or societal.


Transparency and Ethical Considerations

Sponsorship comes with responsibilities. All sponsors must adhere to ethical standards, ensuring participant safety, informed consent, and data integrity. Transparency is critical, particularly for industry-sponsored trials, where conflicts of interest may arise. Initiatives like ClinicalTrials.gov and the World Health Organization’s International Clinical Trials Registry Platform promote public access to trial information, fostering trust.


The Future of Clinical Trial Sponsorship

The landscape of clinical trial sponsorship is evolving, driven by technological advancements and global health challenges. Key trends include:

Decentralized Trials: Digital tools and remote monitoring reduce costs, potentially attracting new sponsors.
Precision Medicine: Trials targeting specific genetic profiles require innovative funding models.
Global Collaboration: International partnerships address pandemics and neglected diseases, pooling resources across borders.

Emerging sponsors, such as tech companies (e.g., Google’s Verily) and patient-driven initiatives, are also entering the space, diversifying the funding ecosystem.

Clinical trials are a cornerstone of medical progress, and their sponsors play a pivotal role in shaping the future of healthcare. From pharmaceutical giants to government agencies, academic institutions to nonprofits, and even individual donors, each sponsor brings unique motivations and resources to the table. Understanding who sponsors clinical trials reveals the complex interplay of science, economics, and ethics that drives innovation. As the field evolves, collaborative and innovative sponsorship models will continue to accelerate the development of life-saving treatments, benefiting patients worldwide.

By shedding light on the funding behind clinical trials, we gain a deeper appreciation for the collective effort required to turn scientific discoveries into tangible solutions. Whether you’re a patient, researcher, or simply curious, recognizing the diverse sponsors of clinical trials underscores the shared commitment to advancing human health.

Who Sponsors Clinical Trials? Read More »