Pharma Operations

Pharma Operations

Building a Strong Quality Management System

Dr. Sarah Ahmed

Karachi, Pakistan


Introduction

Every organization promises something to its customers: a product that works, a service that arrives on time, a result that can be trusted. A Quality Management System (QMS) is how an organization turns that promise into a repeatable reality. It is the set of policies, processes, responsibilities, and records that direct and control how an organization meets customer and regulatory requirements and improves over time.

Many organizations treat quality as a department, a binder of procedures, or a certificate on the wall. Those organizations often find that quality problems keep returning no matter how many procedures they write. A strong QMS is different. It is woven into daily work, supported by leadership, and built around learning from data and mistakes.

This article explains what makes a QMS strong, the core building blocks, a practical path to implementation, and the pitfalls that commonly undermine even well-intentioned efforts.


1. What a Quality Management System Really Is

A QMS is not a single document or software tool. It is an integrated system that answers a few fundamental questions:

  • What do our customers and regulators require of us?
  • What processes must we run to meet those requirements?
  • Who is responsible for each process, and how do we know it is working?
  • What do we do when something goes wrong?
  • How do we get better over time?

The international standard ISO 9001:2015 describes a QMS framework that can be applied to any organization, regardless of size or sector. Regulated industries add their own requirements on top. Medical device manufacturers follow ISO 13485, pharmaceutical manufacturers follow Good Manufacturing Practice and ICH Q10, and other sectors such as aerospace and automotive have their own standards. The underlying logic across all of them is the same: define your processes, control them, measure them, and improve them.


2. The Seven Quality Management Principles

ISO 9000:2015 and ISO 9001:2015 rest on seven principles that serve as the philosophical foundation of a strong QMS:

  1. Customer focus. The primary aim is to meet customer requirements and strive to exceed expectations. Every other principle serves this one.
  2. Leadership. Leaders establish unity of purpose and direction and create conditions in which people are engaged in achieving quality objectives.
  3. Engagement of people. Competent, empowered, and engaged people at all levels are essential to creating and delivering value.
  4. Process approach. Consistent and predictable results are achieved when activities are understood and managed as interrelated processes that function as a coherent system.
  5. Improvement. Successful organizations have an ongoing focus on improvement.
  6. Evidence-based decision making. Decisions based on the analysis and evaluation of data are more likely to produce desired results.
  7. Relationship management. Organizations manage their relationships with interested parties, such as suppliers, to sustain success.

These are not slogans. Each one translates into specific system requirements, and a QMS that ignores any of them tends to develop weak spots. For example, a system with excellent procedures but disengaged leadership will stall, and a system with strong leadership but poor data will make decisions on guesswork.


3. Leadership: The Foundation of Everything

The single most important factor in a strong QMS is top management commitment. Quality systems fail most often not because the procedures are flawed but because leadership treats quality as someone else’s job.

Effective leaders do several things:

  • Set a clear quality policy that reflects the organization’s purpose and is communicated and understood at every level.
  • Establish measurable quality objectives aligned with business strategy, such as reducing customer complaints by a defined percentage or improving on-time delivery.
  • Provide resources, including people, time, training, equipment, and technology.
  • Assign clear roles and authorities, including a quality function with enough independence and standing to raise concerns without fear.
  • Participate in management review, using the meeting to make real decisions rather than rubber-stamp reports.
  • Model the behavior they expect. If leaders bypass procedures under schedule pressure, employees will learn that quality is optional.

A useful test is to ask what happens when quality conflicts with a shipment deadline. The answer reveals the true priorities of the organization, regardless of what the policy says.


4. Understanding Context, Stakeholders, and Scope

A QMS should be designed for the organization it serves rather than copied from a template. ISO 9001 asks organizations to begin by understanding their context: the internal and external factors that affect their ability to deliver quality results. These include market conditions, technology, regulatory changes, organizational culture, and resource constraints.

Organizations must also identify interested parties (customers, regulators, employees, suppliers, shareholders, and the community) and determine which of their needs and expectations become requirements. This analysis then defines the scope of the QMS, meaning which products, services, sites, and processes it covers.

Skipping this step is a common mistake. A scope that is too narrow leaves important risks unmanaged, and a scope that is too broad creates bureaucracy without benefit. Time spent here saves rework later.


5. The Process Approach

A strong QMS treats the organization as a network of processes, each with inputs, activities, outputs, owners, and performance measures. Rather than organizing quality around departments, the process approach follows work as it flows from customer need to customer satisfaction.

Building a process-based system typically involves:

  • Mapping core processes, such as design and development, purchasing, production or service delivery, inspection and testing, and complaint handling.
  • Identifying support processes, such as training, maintenance, calibration, document control, and information technology.
  • Defining interactions, meaning where the output of one process becomes the input of another.
  • Assigning process owners who are accountable for performance and improvement.
  • Setting process metrics, such as yield, defect rate, cycle time, or first-pass success.

Process maps, flowcharts, and SIPOC diagrams (Suppliers, Inputs, Process, Outputs, Customers) are helpful tools. The goal is clarity: anyone should be able to see how work moves through the organization and where quality is won or lost.


6. Risk-Based Thinking

Modern quality standards put risk at the center of the system. ISO 9001:2015 builds risk-based thinking into planning, and ICH Q9 offers a detailed framework for Quality Risk Management in pharmaceutical settings. The idea is simple: anticipate what could go wrong and focus effort where the consequences would be greatest.

A practical risk approach includes:

  • Identifying risks and opportunities at the organizational, process, and product levels.
  • Assessing the likelihood and severity of each, often using a scoring matrix.
  • Prioritizing and deciding whether to eliminate, reduce, transfer, or accept each risk.
  • Planning actions proportionate to the risk, then integrating them into the QMS.
  • Reviewing risks regularly, because they change as products, suppliers, and markets change.

Tools such as FMEA (Failure Mode and Effects Analysis) and HACCP help structure this thinking. A well-run risk process prevents the trap of treating every issue as equally urgent, which wastes resources and dilutes attention from what matters most.


7. Documented Information and Document Control

Documentation is often what people picture when they think of a QMS, and for good reason. Documents communicate requirements, ensure consistency, and provide evidence that work was done as intended. But more documentation does not mean a stronger system.

A strong approach follows these principles:

  • Document what adds value. Write procedures where consistency matters, where errors are costly, or where regulations require them.
  • Keep them usable. Procedures should be short, clear, and written in language that operators actually use. Visuals, checklists, and work instructions often work better than long prose.
  • Control versions. Only current, approved documents should be available at points of use, and obsolete ones should be withdrawn.
  • Maintain records. Records such as inspection results, training files, calibration certificates, and audit reports demonstrate that the system is working.
  • Protect integrity. Records should be accurate, legible, secure, and retrievable for their required retention period. In regulated industries, electronic records need validated systems, access control, and audit trails.

A good test of documentation quality is whether the people doing the work helped write it and can follow it without a supervisor explaining it.


8. People, Competence, and Culture

Even the best-designed system depends on the people who run it. Building competence and culture is therefore central.

Competence. Organizations should define the skills and knowledge each role requires, assess gaps, provide training, and evaluate whether the training worked. Attendance at a session is not proof of competence. Observation, testing, and performance data are better indicators.

Awareness. Employees should understand the quality policy, how their work affects quality objectives, and the consequences of not following requirements.

Communication. Information must flow in all directions. Frontline staff often see problems first, so there must be safe and simple ways to raise them.

Culture. A strong quality culture is one where people take ownership, report errors openly, and focus on fixing systems rather than blaming individuals. Blame-heavy cultures drive problems underground, which is one of the most dangerous conditions for any QMS. When employees fear punishment, deviations go unreported, and small issues grow into major failures.

Leaders can build culture by recognizing good catches, closing the loop on employee suggestions, and treating investigations as learning opportunities.


9. Supplier and Outsourced Process Control

Few organizations make everything themselves. Raw materials, components, software, testing services, and contract manufacturing all come from outside, and quality problems at suppliers become the organization’s own problems.

A strong QMS manages external providers through:

  • Selection and qualification, based on capability, quality history, financial stability, and regulatory compliance.
  • Clear requirements, communicated through specifications, quality agreements, and purchase terms.
  • Ongoing monitoring, through incoming inspection, scorecards, audits, and performance reviews.
  • Corrective action processes to resolve supplier nonconformities.
  • Risk-based oversight, applying the most control to the most critical suppliers.

In regulated industries, responsibility cannot be outsourced. Manufacturers remain accountable for the quality of products made or tested on their behalf.


10. Operational Control: Delivering Consistent Results

Operational control is where the QMS meets daily work. Whether the output is a product or a service, the organization needs to plan and control delivery so that results are consistent.

Elements of strong operational control include:

  • Clear requirements for each product or service, agreed with the customer.
  • Design and development controls, including defined inputs, reviews, verification, validation, and change management.
  • Controlled conditions, such as qualified equipment, calibrated measuring instruments, suitable environments, and trained personnel.
  • In-process monitoring at critical points, rather than relying only on final inspection.
  • Identification and traceability, so that materials and outputs can be tracked when needed.
  • Handling of nonconforming output, including segregation, evaluation, and disposition so defective items do not reach customers.
  • Change control, ensuring that modifications to processes, materials, or systems are evaluated and approved before implementation.

The guiding idea is prevention. It is far cheaper to build quality into a process than to detect defects afterward and far cheaper still than to handle a recall or a lost customer.


11. Measuring Performance: Data, Audits, and Management Review

You cannot manage what you do not measure. A strong QMS uses data to see whether it is working and to drive decisions.

Key Performance Indicators

Useful quality metrics vary by organization but often include:

  • Customer satisfaction and complaint rates.
  • First-pass yield and defect rates.
  • On-time delivery.
  • Cost of poor quality (scrap, rework, returns, warranty).
  • Supplier performance.
  • Audit findings and closure times.
  • CAPA effectiveness and recurrence rates.

Metrics should be few enough to be understood, tied to objectives, and reviewed regularly. A dashboard full of numbers nobody acts on is worse than no dashboard.

Internal Audits

Internal audits, guided by ISO 19011, check whether the QMS conforms to requirements and is effectively implemented. Good audits go beyond box-ticking. They follow real processes, interview people, and examine evidence. Audit programs should be risk-based, giving more attention to high-risk or poorly performing areas, and auditors should be objective and trained.

Management Review

At planned intervals, top management reviews the QMS to confirm it remains suitable, adequate, and effective. Inputs include audit results, customer feedback, process performance, status of corrective actions, supplier performance, and changes in context or risk. The output should be concrete decisions about improvements, resource needs, and changes to the system.


12. Nonconformity, Corrective Action, and Continual Improvement

Problems are inevitable. What distinguishes a strong QMS is how it responds to them.

Correction deals with the immediate problem, such as quarantining a defective batch. Corrective action goes further by eliminating the cause to prevent recurrence. Preventive action, reflected in modern standards through risk-based thinking, addresses potential problems before they occur.

An effective CAPA process includes:

  1. Clear problem definition, with facts rather than assumptions.
  2. Containment, to protect customers and patients.
  3. Root cause analysis, using tools such as the 5 Whys, fishbone (Ishikawa) diagrams, or fault tree analysis.
  4. Action planning, with owners and due dates.
  5. Implementation and verification, confirming that the actions were completed.
  6. Effectiveness checks, confirming that the problem has not returned.

Weak CAPA systems are a leading cause of regulatory findings. Common failures include stopping at “operator error” as the root cause, closing actions without verifying results, and letting overdue actions pile up.

Continual improvement extends beyond fixing failures. The Plan-Do-Check-Act (PDCA) cycle provides a simple engine for it: plan a change, test it, check the results, and standardize what works. Lean, Six Sigma, and Kaizen methods offer additional structured approaches to eliminating waste and variation.


13. Technology and Digital Tools

Electronic quality management software can make a QMS more efficient and transparent. Modern platforms integrate document control, training management, deviation and CAPA tracking, audit management, supplier quality, and analytics in one place.

Benefits include faster workflows, automatic reminders, better traceability, and real-time visibility into quality performance. Advanced analytics can highlight trends that humans might miss, such as early signs of equipment drift or rising defect rates at a particular supplier.

However, technology does not fix a broken process. Digitizing a confusing procedure only makes the confusion faster. Organizations should simplify and standardize processes first, then choose tools that fit. In regulated settings, software used for quality records must also be validated and meet data integrity expectations.


14. A Practical Roadmap to Build a QMS

For organizations starting from scratch or rebuilding, a phased approach works best:

Phase 1: Commit and plan. Secure leadership commitment, appoint a quality lead, define scope, and identify applicable standards and regulations.

Phase 2: Assess the current state. Perform a gap analysis against the chosen standard to see what exists, what is missing, and what is not working.

Phase 3: Design the system. Map processes, define ownership, set the quality policy and objectives, and identify risks. Keep the design as simple as the organization allows.

Phase 4: Document and train. Develop the necessary procedures and records with input from the people who do the work, then train everyone on their responsibilities.

Phase 5: Implement. Run the processes, collect records, and refine procedures based on real-world experience.

Phase 6: Verify. Conduct internal audits and a management review to confirm the system works and to find weaknesses.

Phase 7: Certify or seek approval (if applicable). Undergo a third-party certification audit or regulatory inspection.

Phase 8: Sustain and improve. Keep monitoring, auditing, and improving. A QMS is never finished.

Expect the initial build to take several months for a small organization and longer for a large or highly regulated one. Rushing tends to produce paper systems that look good but are not used.


15. Common Pitfalls to Avoid

Even well-meaning organizations stumble on predictable problems:

  • Quality as a department, not a shared responsibility. When only the quality team cares about quality, the system becomes policing rather than prevention.
  • Over-documentation. Excessive procedures that no one reads or follows create a gap between paper and practice.
  • Copy-and-paste systems. Templates adopted without adaptation fail to reflect how work is actually done.
  • Audit-driven compliance. Systems that come alive only before an audit collapse in between.
  • Ignoring data. Collecting metrics without analyzing or acting on them wastes effort.
  • Superficial root cause analysis. Blaming individuals allows the underlying system flaw to persist.
  • Neglecting change management. Uncontrolled changes to processes, suppliers, or software are a frequent source of unexpected failures.
  • Lack of follow-through. Actions that are assigned but never verified make the system look healthy while problems grow.

Avoiding these comes down to honesty, simplicity, and discipline. The QMS should reflect reality, be as simple as possible, and be used every day.


Conclusion

A strong Quality Management System is not built by writing procedures alone. It grows from committed leadership, a clear understanding of customer and regulatory needs, well-defined processes, sensible risk management, competent and engaged people, reliable data, and a culture that treats problems as opportunities to learn. Each element supports the others. Processes without leadership drift, leadership without data guesses, and data without a culture of openness never tells the full story.

Organizations that invest in a real QMS gain more than certificates or clean inspection reports. They see fewer defects, less rework, more satisfied customers, stronger supplier relationships, and greater resilience when conditions change. Most importantly, they build the trust that every customer, patient, and regulator places in them.

Quality is not a destination but a continuing practice. The organizations that thrive are those that keep asking how they can do things better, and build systems that make the answer part of everyday work.


Guideline References

  1. ISO 9001:2015 – Quality management systems – Requirements.
  2. ISO 9000:2015 – Quality management systems – Fundamentals and vocabulary.
  3. ISO 9004:2018 – Quality management – Quality of an organization – Guidance to achieve sustained success.
  4. ISO 19011:2018 – Guidelines for auditing management systems.
  5. ISO 31000:2018 – Risk management – Guidelines.
  6. ISO 10002:2018 – Quality management – Customer satisfaction – Guidelines for complaints handling in organizations.
  7. ISO 13485:2016 – Medical devices – Quality management systems – Requirements for regulatory purposes.
  8. ICH Q9 (R1) – Quality Risk Management.
  9. ICH Q10 – Pharmaceutical Quality System.
  10. US FDA, 21 CFR Part 820 – Quality Management System Regulation (QMSR), incorporating ISO 13485:2016 by reference.
  11. US FDA, 21 CFR Parts 210 and 211 – Current Good Manufacturing Practice for Finished Pharmaceuticals.
  12. European Commission, EudraLex Volume 4, Part I, Chapter 1 – Pharmaceutical Quality System.
  13. WHO Technical Report Series No. 986, Annex 2 – WHO Good Manufacturing Practices for Pharmaceutical Products: Main Principles.

Building a Strong Quality Management System Read More »

Understanding Pharmaceutical Manufacturing Processes

Dr. John Smith

CA, USA


Introduction

Every tablet, capsule, injection, or syrup a patient takes is the result of a tightly controlled, multi-stage manufacturing process. Unlike many consumer goods, medicines must deliver the right amount of active ingredient, in the right form, every time, and small deviations can affect safety and efficacy. Pharmaceutical manufacturing is therefore as much a discipline of quality and control as it is of chemistry and engineering.

This article walks through the main stages of pharmaceutical manufacturing, from sourcing raw materials to releasing the finished product. It also explains the quality frameworks that govern these processes and the trends reshaping the industry.


1. The Big Picture: From Molecule to Medicine

Pharmaceutical manufacturing can be divided into two broad phases:

  1. Primary manufacturing, which produces the active pharmaceutical ingredient (API), also called the drug substance. This happens through chemical synthesis, fermentation, extraction from natural sources, or biotechnological processes using living cells.
  2. Secondary manufacturing, which converts the API into a finished dosage form (the drug product), such as tablets, capsules, liquids, creams, or injectables, and packages it for distribution.

Around both phases sits a quality system covering raw material testing, in-process controls, validation, documentation, and final release. The guiding principle is that quality cannot be tested into a product. It must be built into the process by design.


2. Product Development and Technology Transfer

Before commercial manufacturing begins, a product passes through development. Formulation scientists study the API’s physical and chemical properties, including solubility, particle size, polymorphism, stability, and compatibility with excipients (the inactive ingredients). These studies determine which dosage form is feasible and what manufacturing route will produce it consistently.

Modern development follows the Quality by Design (QbD) approach described in ICH Q8. Developers begin by defining a Quality Target Product Profile (QTPP), which sets out the intended characteristics of the final product. From it they identify Critical Quality Attributes (CQAs), such as assay, dissolution, content uniformity, and impurity levels. They then determine which Critical Material Attributes (CMAs) and Critical Process Parameters (CPPs) influence those attributes. Experiments, often using Design of Experiments (DoE), establish a design space: the range of input variables within which quality is assured.

Once a process is developed at laboratory and pilot scale, it undergoes technology transfer to the commercial site. This step moves knowledge, specifications, analytical methods, and process understanding from the development team to manufacturing, and it is a frequent source of scale-up problems. A well-documented transfer reduces the risk of failed batches and regulatory delays.


3. Raw Materials and Supplier Control

The quality of a medicine begins with its ingredients. Manufacturers source APIs, excipients, solvents, and packaging components from qualified suppliers, and each supplier goes through an approval process that may include audits, questionnaires, and sample testing.

On receipt, materials are:

  • Quarantined until tested and approved.
  • Sampled using statistically justified plans.
  • Tested against approved specifications for identity, purity, and other relevant attributes.
  • Labeled and stored under defined conditions of temperature, humidity, and light.

Only released materials may be used in production. Identity testing is especially important because supply chain mix-ups and adulteration have caused serious public health incidents in the past.


4. Manufacturing the Active Pharmaceutical Ingredient

Chemical Synthesis

Most small-molecule drugs are made through multi-step organic synthesis. Starting materials react in a controlled sequence to build the target molecule, with intermediates isolated and tested along the way. Key unit operations include:

  • Reaction: controlled addition of reagents, catalysts, and solvents in reactors, with attention to temperature, pressure, and mixing.
  • Separation and extraction: removing by-products and unreacted materials.
  • Crystallization: forming the solid API with the desired particle size and crystal form (polymorph).
  • Filtration and drying: isolating and removing residual solvents.
  • Milling and micronization: adjusting particle size, which can strongly affect dissolution and bioavailability.

Impurity control is central. Regulators expect manufacturers to identify, quantify, and limit organic impurities, residual solvents, and elemental impurities in line with ICH Q3A through Q3D.

Biotechnological APIs

Biologics such as monoclonal antibodies, vaccines, and recombinant proteins are produced by living systems, typically mammalian cells, bacteria, or yeast. The process has two main stages:

  • Upstream processing: growing cells in bioreactors under controlled conditions so they express the desired protein.
  • Downstream processing: harvesting, purifying (through chromatography and filtration), and formulating the product, including viral clearance steps where required.

Because biologics are large, complex molecules, the process largely defines the product. Even small changes in cell culture conditions can alter the final molecule’s characteristics.

ICH Q7 provides the GMP framework for APIs and is widely recognized as the international standard for API manufacturing.


5. Manufacturing the Finished Dosage Form

Oral Solid Dosage Forms

Tablets and capsules remain the most common dosage forms. A typical tablet process includes:

  1. Dispensing and weighing: each material is weighed and verified, often with a second-person check or an electronic system.
  2. Sieving and milling: ensuring uniform particle size and breaking up lumps.
  3. Blending: mixing the API and excipients to achieve content uniformity.
  4. Granulation: converting powder into granules to improve flow and compressibility. Wet granulation uses a liquid binder followed by drying. Dry granulation uses roller compaction. Direct compression skips granulation when the blend flows and compresses well enough on its own.
  5. Compression: forming tablets on a rotary press, with weight, hardness, thickness, and friability monitored.
  6. Coating: applying a film coat for taste masking, protection, appearance, or modified release.
  7. Capsule filling: for capsules, filling powder, granules, or pellets into hard gelatin or other shells.

Finished tablets are tested for dissolution, disintegration, assay, and content uniformity.

Liquid Oral Dosage Forms

Syrups, suspensions, and solutions involve dissolving or dispersing the API in a vehicle, along with preservatives, sweeteners, flavors, and buffers. Critical controls include mixing order, temperature, pH, viscosity, and microbial quality. Suspensions also require attention to particle settling and redispersibility.

Semi-Solid Dosage Forms

Creams, ointments, and gels are made by heating and combining oil and water phases, often with emulsifiers, then homogenizing and cooling under controlled conditions. Rheology, droplet size, and homogeneity are key quality attributes.

Sterile Products

Injectables, ophthalmic preparations, and some other products must be sterile. Sterile manufacturing is among the most demanding areas of the industry and follows one of two routes:

  • Terminal sterilization: the product is filled and sealed, then sterilized in its final container, usually by steam (autoclave). This is preferred when the product can tolerate heat.
  • Aseptic processing: the product and its container components are sterilized separately, then filled and sealed in an aseptic environment. This is used for heat-sensitive products, including many biologics.

Aseptic manufacturing requires classified cleanrooms, unidirectional airflow, rigorous gowning, environmental monitoring, and media fill simulations that demonstrate the process can maintain sterility. Increasingly, manufacturers use isolators and restricted access barrier systems (RABS) to separate operators from the product. The revised EU GMP Annex 1 (2022) emphasizes a holistic Contamination Control Strategy for sterile manufacturing.

Lyophilization (freeze-drying) is used for products unstable in solution. It removes water by sublimation under vacuum, yielding a stable powder for reconstitution.


6. Packaging and Labeling

Packaging is not an afterthought. It protects the product from moisture, oxygen, and light, and it carries the information patients and clinicians depend on. Packaging operations include:

  • Primary packaging: blisters, bottles, vials, ampoules, syringes, or sachets in direct contact with the product.
  • Secondary packaging: cartons, leaflets, and shipping cases.
  • Labeling and serialization: printing batch numbers, expiry dates, and, increasingly, unique identifiers to combat counterfeiting and support traceability.

Mix-ups are a major risk here. Controls such as line clearance, label reconciliation, automated vision inspection, and barcode verification prevent the wrong label or leaflet from reaching the wrong product. Packaging is also studied for compatibility with the product through stability testing under ICH Q1A conditions.


7. Quality Control, Quality Assurance, and Batch Release

Quality Control (QC) and Quality Assurance (QA) work together but have distinct roles.

Quality Control performs the testing: raw material analysis, in-process checks, finished product testing, stability studies, and microbiological and environmental monitoring. Analytical methods must be validated for accuracy, precision, specificity, linearity, and robustness (ICH Q2).

Quality Assurance oversees the overall system. It reviews batch records, approves procedures, manages deviations, change control, and corrective and preventive actions (CAPA), conducts internal audits, and ultimately authorizes batch release.

Before a batch is released, QA reviews the complete batch manufacturing record, confirms all tests met specifications, verifies that any deviations were investigated and closed, and checks that the process ran within validated parameters. Only then is the product released for distribution.


8. Process Validation and Cleaning Validation

Process validation provides documented evidence that a process consistently produces a product meeting its predetermined specifications. The modern lifecycle approach, described in regulatory guidance, has three stages:

  1. Process design: defining the commercial process based on development knowledge.
  2. Process qualification: confirming the process performs as intended at commercial scale, including qualification of facilities, utilities, and equipment.
  3. Continued process verification: ongoing monitoring during routine production to confirm the process remains in a state of control.

Cleaning validation addresses cross-contamination in multi-product facilities. Manufacturers must show that cleaning procedures reliably remove product residues, cleaning agents, and microbial contamination to acceptable limits. These limits are increasingly based on toxicological assessments, such as health-based exposure limits.


9. Facilities, Utilities, and Equipment

The manufacturing environment is part of the process. Good facility design supports logical material and personnel flow, prevents cross-contamination, and allows effective cleaning. Key elements include:

  • HVAC systems that control air quality, pressure differentials, temperature, and humidity.
  • Water systems: purified water and Water for Injection (WFI) are critical utilities, continuously monitored for conductivity, total organic carbon, and microbial counts.
  • Compressed gases and steam that contact the product or equipment and must meet quality standards.
  • Qualified equipment: installation, operational, and performance qualification (IQ/OQ/PQ), combined with preventive maintenance and calibration.

10. Documentation and Data Integrity

In pharmaceutical manufacturing the saying goes, “If it isn’t documented, it didn’t happen.” Master formulas, batch records, standard operating procedures, logbooks, and test records form the evidence trail that demonstrates compliance.

Regulators place strong emphasis on data integrity, commonly summarized by the ALCOA+ principles: data should be Attributable, Legible, Contemporaneous, Original, and Accurate, as well as Complete, Consistent, Enduring, and Available. Electronic systems require audit trails, access controls, and validation to ensure records are trustworthy.


11. Regulatory Oversight and Quality Risk Management

Manufacturers operate under GMP regulations enforced by authorities such as the US FDA, the European Medicines Agency and national EU authorities, the UK MHRA, and many others, with harmonization efforts through ICH, WHO, and PIC/S. Regular inspections verify compliance, and serious findings can lead to warning letters, import bans, or product recalls.

Quality Risk Management (ICH Q9) gives a systematic way to assess and control risks to product quality. Tools such as Failure Mode and Effects Analysis (FMEA) and Hazard Analysis and Critical Control Points (HACCP) help companies focus resources on the highest-risk areas. ICH Q10 adds a model for a Pharmaceutical Quality System built on management responsibility and continual improvement.


12. Emerging Trends in Pharmaceutical Manufacturing

The industry is changing, driven by demands for efficiency, flexibility, and resilience.

Continuous manufacturing replaces traditional batch-by-batch production with an uninterrupted flow from raw materials to finished product. It can reduce footprint, shorten production time, and allow real-time quality monitoring.

Process Analytical Technology (PAT) uses in-line or at-line sensors, such as near-infrared spectroscopy, to monitor quality during production. This supports real-time release testing and reduces dependence on end-product testing.

Advanced therapies, including cell and gene therapies, require individualized, often small-scale manufacturing with tight timelines and complex logistics.

Digitalization and Industry 4.0 technologies, including manufacturing execution systems, electronic batch records, data analytics, and machine learning, improve traceability and help predict equipment issues before they cause failures.

3D printing is being explored for personalized dosing and complex release profiles.

Green chemistry and sustainability efforts aim to reduce solvent use, waste, and energy consumption across the lifecycle.


13. Common Challenges

Despite technological progress, manufacturers face persistent challenges:

  • Supply chain vulnerability: dependence on limited suppliers for critical materials can cause shortages.
  • Scale-up difficulties: processes that work in the lab may behave differently at commercial scale.
  • Contamination and cross-contamination: especially in multi-product facilities and sterile operations.
  • Regulatory complexity: requirements differ across regions, complicating global supply.
  • Skilled workforce: advanced processes require trained personnel with both technical and quality expertise.
  • Cost pressure: particularly for generics, where margins are thin but quality expectations are unchanged.

Addressing these requires a strong quality culture in which everyone, from operators to senior management, understands that patient safety comes first.


Conclusion

Pharmaceutical manufacturing combines science, engineering, and rigorous quality management. It begins with carefully controlled raw materials and API production, moves through formulation and dosage form manufacture, and ends with packaging, testing, and release, all under a system that documents every step. Concepts such as Quality by Design, process validation, risk management, and data integrity are the foundation of consistent product quality.

As continuous manufacturing, real-time monitoring, and digital tools mature, the industry is moving toward processes that are more efficient, more flexible, and better understood. Through all these changes the goal stays the same: delivering safe, effective, high-quality medicines to every patient, every time.


Guideline References

  1. ICH Q7 – Good Manufacturing Practice Guide for Active Pharmaceutical Ingredients.
  2. ICH Q8 (R2) – Pharmaceutical Development.
  3. ICH Q9 (R1) – Quality Risk Management.
  4. ICH Q10 – Pharmaceutical Quality System.
  5. ICH Q11 – Development and Manufacture of Drug Substances.
  6. ICH Q1A (R2) – Stability Testing of New Drug Substances and Products.
  7. ICH Q2 (R2) – Validation of Analytical Procedures.
  8. ICH Q3A–Q3D – Impurities: new drug substances and products, residual solvents, and elemental impurities.
  9. US FDA, 21 CFR Part 210 and Part 211 – Current Good Manufacturing Practice for Finished Pharmaceuticals.
  10. US FDA (2011) – Guidance for Industry: Process Validation: General Principles and Practices.
  11. European Commission, EudraLex Volume 4 – EU Guidelines for Good Manufacturing Practice for Medicinal Products for Human and Veterinary Use, including Annex 1 (Manufacture of Sterile Medicinal Products) and Annex 15 (Qualification and Validation).
  12. WHO Technical Report Series No. 986, Annex 2 – WHO Good Manufacturing Practices for Pharmaceutical Products: Main Principles.
  13. PIC/S PE 009 – Guide to Good Manufacturing Practice for Medicinal Products.
  14. PIC/S PI 041 and US FDA guidance on Data Integrity and Compliance with Drug CGMP.
  15. US FDA (2004) – Guidance for Industry: PAT, A Framework for Innovative Pharmaceutical Development, Manufacturing, and Quality Assurance.

Understanding Pharmaceutical Manufacturing Processes Read More »

How Do Pharmaceutical Companies Make Money?

Pharmaceutical companies make money by discovering, developing, and commercializing medicines that address unmet medical needs. Their core business model is built around patented prescription drugs, but revenue also comes from vaccines, over-the-counter products, licensing, partnerships, and services. Below is a clear, up-to-date breakdown of where the money comes from, how prices are set, what patents really do, and the key risks and trends shaping pharma profits.


Who actually pays for medicines?

  • United States: A mix of commercial insurers, Medicare/Medicaid, pharmacy benefit managers (PBMs), employers, and patients (copays/coinsurance). PBMs negotiate rebates from manufacturers.
  • Europe and many other countries: Central or regional health systems negotiate prices, often with health technology assessment (HTA) bodies (e.g., NICE in the UK).
  • Low- and middle-income countries: Government tenders, international organizations, and differential pricing strategies often apply.


The core engine: Patented prescription drugs

  • Innovation drives value: Most revenue comes from branded drugs protected by patents/data exclusivity. These drugs command higher prices due to novelty, clinical benefit, and lack of direct competition.
  • Specialty focus: Over the past decade, growth has shifted toward specialty and rare-disease therapies (oncology, immunology, gene/cell therapy), which often serve smaller populations at higher per-patient prices.
  • Blockbusters: A small number of products can contribute a disproportionate share of total revenue and profits.


Mindfulness and Meditation Techniques

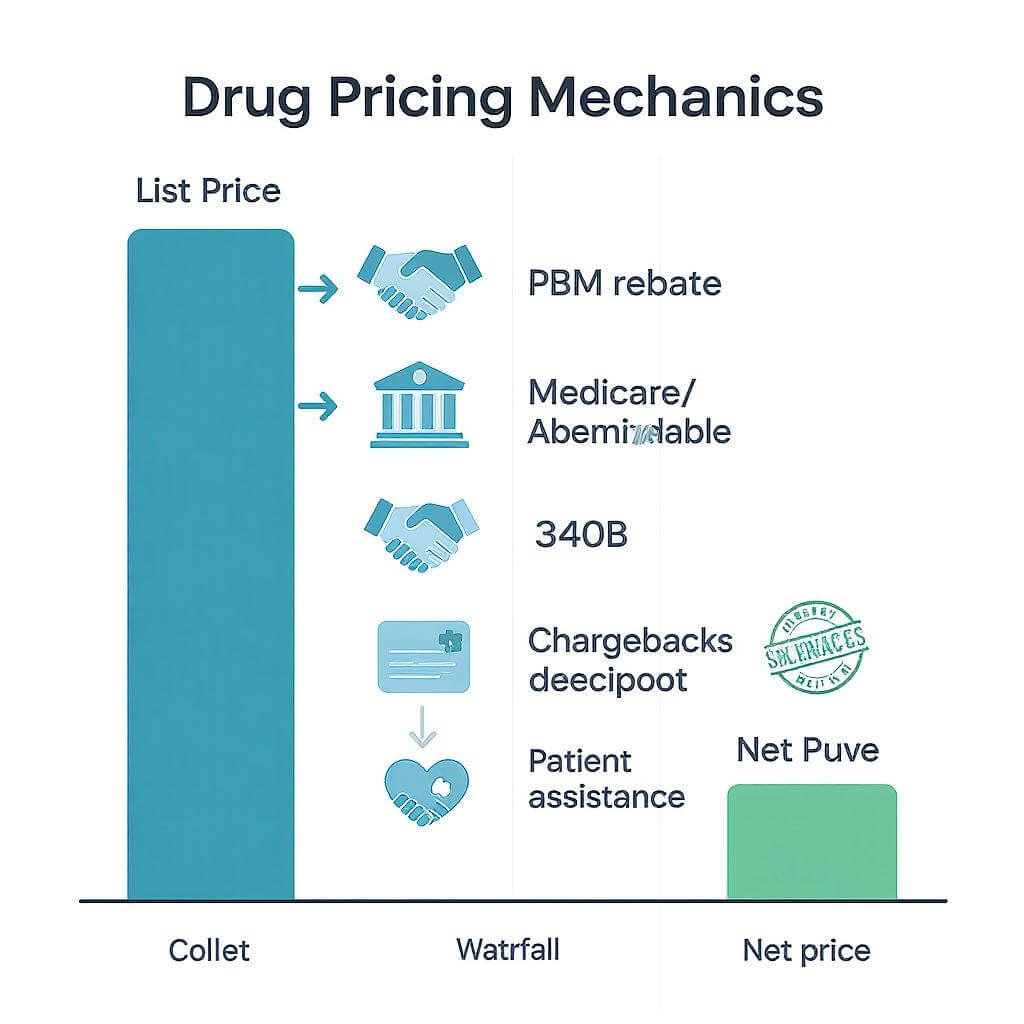
How pricing works (and why “list price” isn’t what it seems)

  • List price vs. net price: In the U.S., manufacturers set a list price (WAC), but pay mandatory and negotiated discounts: rebates to PBMs/insurers, government discounts (Medicaid, 340B), chargebacks, and patient support. Net price = list price minus all these concessions.
  • The “gross-to-net” gap: For many branded drugs in the U.S., net price can be 30–60% below list price, depending on the product and payer mix.
  • Outside the U.S.: Prices are usually negotiated nationally, subject to reference pricing and value assessments, often resulting in lower net prices than in the U.S.

Patents and exclusivity protect profits (for a time)

  • Patents: Typically last 20 years from filing. Because filing often occurs early in development, effective post-approval exclusivity is often 7–12 years.
  • Regulatory exclusivity (U.S.): New Chemical Entity (5 years), biologics (12 years), orphan drugs (7 years), pediatric exclusivity (6 months), plus various add-ons. EU uses “8+2+1” data/market protection.
  • Lifecycle management: Companies extend value via new indications, pediatric studies, new formulations (e.g., extended release), device-drug combos, and authorized generics.

The R&D pipeline economics

  • High risk, high cost: Only a minority of candidates that enter human trials achieve approval. Industry-wide, roughly 1 in 10 (varies by therapy area) successfully reach market.
  • Timelines: Discovery and preclinical can take 3–6 years; clinical development and review often add 6–10 years.
  • Investment scale: Total cost to develop an approved medicine varies widely (hundreds of millions to several billions of dollars, depending on modality and failure-adjusted costs).
  • Portfolio logic: A few big winners often offset many failures—one reason companies value platforms and scalable science (e.g., mRNA, antibodies).

Market access, sales, and promotion

  • Access matters as much as science: Formulary placement, prior authorizations, and step therapy affect uptake.
  • PBMs and rebates (U.S.): Manufacturers negotiate rebates for preferred formulary tiers; better placement can drive volume but reduce net price.
  • Promotion: Engagement with healthcare professionals (education, field teams), medical conferences, and—mainly in the U.S. and New Zealand—direct-to-consumer advertising.

After exclusivity: Generics and biosimilars

  • Small-molecule generics: Rapid price erosion and market share loss for the brand when generics launch; margins compress significantly.
  • Biologics and biosimilars: Competition grows more gradually than with pills; price erosion is meaningful but typically slower and less steep than small molecules.
  • Authorized generics: The brand company may sell a “generic” version to retain some share as prices fall.

Other revenue streams beyond branded Rx

  • Vaccines: High-volume, tender-driven in many markets; strategic for public health and reputation.
  • Consumer health/OTC: Pain relief, allergy, vitamins, skincare. Some big pharmas have spun these into separate companies, but it remains a revenue category for many.
  • Licensing and royalties: Upfront payments, milestones, and ongoing royalties from out-licensing or co-developing assets and platforms.
  • Collaborations and co-promotion: Shared risk and reward with biotech or other pharmas.
  • Contract manufacturing (CDMO/CMO): Select companies monetize capacity by producing for third parties (more common among specialized manufacturers).
  • Diagnostics and devices: Companion diagnostics can support therapy adoption; some firms bundle device-drug solutions (e.g., auto-injectors).

Regional pricing and market dynamics

  • United States: Higher net prices on average; complex rebates; significant role for PBMs; DTC advertising allowed.
  • Europe: Centralized or HTA-driven price negotiations; outcomes- and value-based agreements are increasingly used.
  • Emerging markets: Volume-driven, tender-based, and differential pricing; growth opportunities with expanding access.

What the P&L often looks like (ranges vary by company and product)

  • Revenue: Volume × net price (after discounts).
  • Cost of goods sold (COGS): Often 5–10% of sales for small-molecule tablets; can be 15–30% for biologics due to complex manufacturing.
  • R&D expense: Frequently 15–25% of sales for large R&D-based companies.
  • SG&A (sales, general, administrative): Often 25–35% of sales, driven by field forces, marketing, and market access activities.
  • Operating margin: Commonly 20–30% for large, diversified companies; varies widely based on mix and lifecycle stage.

Key risks and headwinds

  • Patent cliffs and biosimilar waves
  • Regulatory and price pressures (e.g., U.S. Medicare price negotiations, EU reference pricing)
  • Clinical failures and safety issues
  • Competition from alternative therapies and generics
  • Supply chain and manufacturing complexities (especially for biologics)
  • Litigation and compliance risks

Trends reshaping pharma revenue

  • Biologics, cell and gene therapies: High-value, one-time or infrequent dosing models; experimentation with annuity and outcomes-based payments.
  • Precision medicine: Smaller, biomarker-defined populations with strong clinical differentiation.
  • Real-world evidence and value-based contracts: Tying payment to patient outcomes to support access.
  • AI-enabled R&D: Aiming to improve target discovery, trial design, and success rates.
  • Metabolic and obesity therapies: Rapidly expanding markets influencing payer strategies and budgets.

A quick revenue math example

  • Net revenue = treated patients × duration × net price.
  • Suppose a rare-disease therapy is priced at $300,000 per year, with 2,000 treated patients and an average 15% discount. Net price ≈ $255,000. Annual net revenue ≈ 2,000 × $255,000 = $510 million. From this, the company funds manufacturing, R&D, SG&A, taxes, and profit.

FAQs

Q: How do pharma companies set drug prices?

A: They consider clinical value, unmet need, competitive landscape, target population size, development/manufacturing costs, and payer willingness to reimburse. In many countries, negotiated or value-based frameworks set effective prices.

Q: Why are drug prices often higher in the U.S.?

A: The U.S. relies on market-based negotiations among manufacturers, PBMs, and insurers, with fewer national price controls. Rebates reduce net prices, but patient out-of-pocket can still be high depending on benefit design.

Q: Do pharmaceutical companies profit from generics?

A: Brand-focused companies generally see steep revenue declines when generics arrive. Generic-focused companies earn profits through high-volume, low-margin models. Some brands use authorized generics to retain share.

Q: How long do patents protect a drug?

A: Patents last 20 years from filing, but effective post-approval exclusivity is often 7–12 years due to early filing and development time. Additional regulatory exclusivities can extend protection for specific indications or populations.

Q: What is a PBM and why do rebates matter?

A: Pharmacy Benefit Managers negotiate drug coverage and pricing for insurers/employers. Manufacturers pay rebates for preferred formulary placement. Those rebates lower net prices but can complicate patient out-of-pocket costs.

Q: Why do prices sometimes increase annually?

A: Manufacturers may take list price increases to offset rebates/inflation, support ongoing R&D, or align with market dynamics. However, net prices (after discounts) may rise more modestly or even fall, depending on competition and payer leverage.

Q: How did COVID-19 vaccines generate revenue?

A: Through large government procurement contracts, often at negotiated prices per dose. Economics varied by country, volume, and contract terms; profits were influenced by scale, manufacturing efficiency, and partnerships.

Key takeaways

  • Most pharma revenue comes from patented prescription drugs during a limited exclusivity window.
  • Net price—not list price—drives revenue; U.S. gross-to-net discounts are substantial.
  • R&D is costly and risky; a few winners fund many failures.
  • Profits depend on market access, lifecycle strategy, and geographic mix.
  • Generics/biosimilars reset economics post-exclusivity.
  • Licensing, vaccines, OTC, and services provide diversification.
  • Policy and payer trends (e.g., value-based contracts, price negotiations) are reshaping the model.

How Do Pharmaceutical Companies Make Money? Read More »

What is a Drug Shortage?

In our fast world, getting the right meds is key to keep good health. Yet, at times, some drugs can’t be found or are hard to get. This leads to what we call a drug shortage. Such a problem has big effects, touching the lives of sick folk, health care folks, and the drug-making companies. In this piece, we’ll dive into what a drug shortage is, why it happens, its effects, and how we might fix it, giving useful info for those who need to know more.


What is a Drug Shortage?

A drug shortage happens when there’s not enough of a drug to meet the need. This makes it hard, or even impossible, for folks to get the meds they need. These shortages can be about drugs you need a note from the doctor to buy.

Causes of Drug Shortages

Manufacturing Issues: Issues at the places where they make the drugs can cause big problems. If they have trouble making a drug as they should, or if the place that makes drugs breaks, it can hold up how much of the drug is made.

Quality Problems: Sometimes, the drug itself or the things needed to make the drug aren’t good enough to meet safety rules. This leads them to stop making the drug until they fix the issue.

Regulatory Actions: If a drug does not meet the safety rules set by groups like the FDA, EMA, or WHO, they might stop or slow down the making of these drugs.

Supply Chain Issues: Problems in getting the things needed to make the drugs, or in shipping the drugs from one place to another can also lead to shortages.

High Demand: When many more people need a drug than usual, like during a health crisis, it can be hard to have enough for everyone.

Knowing why shortages happen can help us find ways to fix this problem. This ensures that people get the medicines they need when they need them.

How Antibiotic Works

Manufacturing and Supply Chain Issues

Production Delays: Trouble at making sites, such as tool breaks, dirt, or checks on quality, can stop making.

Raw Material Shortages:

Many drugs need key drug parts (APIs) from around the world. Problems in getting these raw parts, often from world politics or big storms, can cause lack.

Supply Chain Disruptions:

The ways goods move around the world are tough, and things like sickness spread, trade limits, or slow transport can stop the move of meds.

Economic Factors

Low Profit Margins: Generic drugs, which cost less, might not bring in much money for those who make them. This could make these companies stop making them or make less.

Market Consolidation:

If just a small number of makers produce a certain drug, any problems in their work can cause big shortages.

Regulatory Challenges

Stringent Regulations: Rules are there to make sure drugs are safe and good, but they can slow down making them if makers can’t meet these rules.

Approval Delays: New makers trying to enter the market might face slow approval times, which can make shortages worse.


Increased Demand

Unexpected Spikes: Sudden jumps in need, like in a health crisis (say, a pandemic or flu hit), can use up drug stores quicker than makers can fill them back up.

Off-Label Use: When drugs are taken for uses they weren’t first made for, it can stretch supplies thin and cause lack of them for people who need them for allowed uses.

Natural Disasters and Crises

Events such as storms, quakes, or widespread disease can harm drug-making places, mess up moving goods, or cut down on workers, all adding to drug shortages.

Impacts of Drug Shortages

Drug shortages can really harm patients, caregivers, and the whole health system. Here are some big bad effects:

Patient Health Risks

Delayed or Interrupted Treatments: Patients might face delays in getting key meds, which can make their health issues worse or lead to other problems.

Substitutions: Doctors might have to use different drugs, which may not work as well or could cause more side effects.

Medication Errors: Without the usual drugs, there may be more mistakes in how much or how drugs are given out, putting patients in danger.

Increased Healthcare Costs

Shortages often make the price of meds go up as the need for them is more than what is available. Doctors might also have to use more time and help to find other options or to take care of patients.

Strain on Healthcare Providers

Doctors, pharmacists, and nurses have more work as they look for other treatments, talk to patients, and deal with problems from shortages.

Public Health Threats

When there is not enough vaccines, antibiotics, or antiviral drugs, it can stop us from fighting infections. This puts our health at risk.


Collaboration

Teams from different countries work together, joining forces between rules makers, makers, and health teams. They help fix supply chain issues and share what they have in hard times.


How Can Patients and Healthcare Providers Cope with Drug Shortages?

If you face a drug shortage, here are easy steps you can take:

For Patients:

Talk to Your Healthcare Provider: Chat with your doctor or pharmacist about other treatment or medicine options.

Get Ready Early: If you can, plan with your drug store to make sure you have enough of your medicine.

Don’t Stock Up Too Much: Saving up too many drugs can make shortages worse, so get only what you need.


For Healthcare Providers:

Stay Informed: Often look at drug lack lists and news from rule groups.

Collaborate: Join hands with drug experts and other helpers to find good and safe other ways.

Educate Patients: Tell your patients about the lacks and include them in making choices about their care.The Future of Drug Shortages: Solutions and Innovations

Dealing with drug shortages needs plans that last long and new ideas. Some ways to fix this include:

Diversifying Supply Chains: Cutting down on depending on just one maker or place for raw items and made drugs.

Advanced Manufacturing Technologies: Putting money into things like ongoing making to make making better and more bendy.

Data Analytics: Using smart guesswork to see shortages coming and handle stock in a good way.

Global Cooperation: Making ties between nations stronger to make sure all get equal chance at meds when there are hard times.

Understanding Drug Shortages


Drug shortages are a big problem that can mess up how we care for the sick, run health care places, and take care of public health. By knowing why they happen, how they affect us, and ways to fix them, we can work to make sure everyone can get the medicines they need, in a fair way. If drug shortages worry you, you should keep up with the news, talk to your doctor, and push for rules that tackle this big issue.


Stay Updated

For the most recent news on drug shortages, look at tools like the FDA’s Drug Shortages Database or talk to your local rules group. By joining hands, we can lessen the bad effects of not having enough drugs and help everyone be healthier.

What is a Drug Shortage? Read More »

Can I Lose Weight by Eating More Frequently in Smaller Portions?

When it comes to losing weight, there’s a world of advice out there: diet plans, exercise routines, intermittent fasting, calorie counting, and the list goes on. But among all these options, one method that has sparked curiosity is the idea of eating more frequently in smaller portions. The basic premise is simple: instead of three large meals, eat several smaller meals throughout the day. But does this approach really help with weight loss?

In this article, we will explore the science behind eating more frequently in smaller portions and whether this strategy can truly help you lose weight. We will examine the potential benefits, debunk common myths, and give you practical tips to decide if this eating strategy is right for your weight loss journey. So, can you really lose weight by eating more frequently? Let’s dive into it.

eating more frequently

The Basics of Weight Loss: A Quick Overview

Before we can fully understand whether eating more frequently in smaller portions can aid weight loss, we need to grasp the fundamental principle behind losing weight: calories in versus calories out. Simply put, to lose weight, you need to consume fewer calories than your body needs to maintain its current weight. This is called a caloric deficit.

The body uses calories for everything it does—breathing, thinking, walking, and digesting food. If you consistently consume more calories than your body burns, the excess calories are stored as fat. Conversely, when you eat fewer calories than your body requires, it begins to use stored fat for energy, leading to weight loss.

Now, let’s explore how eating more frequently might play into this equation.


How Eating More Frequently Works

The idea of eating more frequently is rooted in the belief that consuming smaller meals throughout the day will speed up your metabolism, prevent overeating, and help with portion control. In essence, instead of eating one or two large meals, you eat several smaller meals at regular intervals. The thinking behind this is that smaller meals help to keep your hunger at bay and your metabolism in overdrive.

But does this theory hold water, or is it just another fad diet myth?


Myth #1: Eating More Frequently Boosts Your Metabolism

One of the key arguments for eating more frequently in smaller portions is that it will speed up your metabolism. The theory goes that when you eat, your body has to expend energy to digest and process the food. This energy expenditure is known as the thermic effect of food (TEF).

While it’s true that digestion does require energy, the effect of meal frequency on metabolism isn’t as significant as it may seem. Studies have shown that the thermic effect of food accounts for only about 10% of your total daily calorie expenditure. Whether you eat three meals a day or six smaller meals, the thermic effect of food remains roughly the same. So, eating more frequently won’t drastically increase your metabolism.

However, eating smaller, balanced meals throughout the day can help to maintain stable blood sugar levels, reducing the risk of energy crashes and cravings. This can make it easier to stick to your weight loss goals by preventing overeating and making healthier food choices.


Myth #2: Eating More Frequently Helps Control Hunger and Prevents Overeating

One of the most convincing arguments for eating more frequently in smaller portions is that it helps control hunger and prevent overeating. When you go long periods without food, your hunger hormones ramp up, leading to strong cravings and overeating at your next meal. By eating smaller meals every 3-4 hours, you can theoretically keep hunger at bay and avoid the temptation to overeat.

While there is some truth to this idea, the effectiveness of this approach varies from person to person. For some individuals, eating more frequently can indeed curb hunger and make it easier to control portion sizes. However, for others, the constant eating may lead to mindless snacking or unnecessary calorie consumption. It all comes down to how well you manage your food choices and ensure that each meal is balanced and nutrient-dense.

What are healthy sources for weight loss

Myth #3: Eating More Frequently Helps Stabilize Blood Sugar

Eating smaller, more frequent meals can help stabilize your blood sugar levels, which is particularly important for people with insulin resistance or type 2 diabetes. When you consume large meals, particularly those rich in carbohydrates, your blood sugar levels spike quickly, leading to an insulin response. If your body is constantly exposed to these fluctuations, it can lead to weight gain, fatigue, and poor metabolic health.

By spreading your food intake throughout the day, you help prevent large swings in blood sugar, which can improve energy levels and prevent insulin resistance. This can make it easier for your body to process and use the calories you consume, instead of storing them as fat.


The Potential Benefits of Eating More Frequently in Smaller Portions

So, if eating more frequently in smaller portions doesn’t dramatically boost metabolism or cause significant weight loss by itself, what are the actual benefits of this eating pattern?

1. Improved Portion Control

One of the biggest advantages of eating more frequently in smaller portions is that it can help you manage portion sizes. When you eat larger meals, it’s easy to overeat, especially if you’re distracted or not paying attention to your hunger cues. Eating smaller meals can help you avoid overeating, as you’re less likely to feel overly full or stuffed.

Additionally, smaller meals allow you to focus more on the quality of your food rather than the quantity. You can choose nutrient-dense foods that support weight loss, like vegetables, lean proteins, and whole grains, instead of filling up on empty calories or processed foods.

2. Better Digestion and Absorption of Nutrients

Eating smaller, more frequent meals can also improve your digestion. Large meals can overwhelm your digestive system, leading to bloating, indigestion, and discomfort. By spreading out your meals, your body has more time to digest and absorb nutrients efficiently, which can lead to better overall health and potentially more effective weight loss.

3. Increased Satiety

One of the challenges of losing weight is feeling satisfied after meals. If you’re constantly hungry, it can be hard to stick to your caloric goals. Smaller meals spread throughout the day can help you feel fuller for longer, making it easier to stay within your target calorie range. Eating protein-rich snacks and meals, in particular, can enhance feelings of fullness and reduce cravings.

4. Better Energy Levels

Eating more frequently can help maintain steady energy levels throughout the day. When you eat large meals, your blood sugar can fluctuate, leading to energy crashes. Smaller meals provide your body with a consistent supply of fuel, which can help keep your energy levels stable. This might also make it easier to stay active and stick to your fitness routine, both of which are important for weight loss.

5. Psychological Benefits

For some people, eating more frequently can provide psychological benefits. It allows them to enjoy food more often throughout the day, reducing feelings of deprivation or restriction. This can make the weight loss process feel more sustainable and enjoyable, rather than like a constant struggle.

The Science Behind Eating More Frequently

While eating more frequently might seem like a great strategy, it’s important to understand the science behind the way our bodies process food and burn fat. One of the most significant factors in weight loss is calorie density—the amount of calories in a given weight or volume of food.

If you eat smaller meals more frequently but don’t watch the overall calorie content of those meals, you could end up eating more calories than you need. For example, if you snack on high-calorie foods throughout the day, you may not be able to achieve the caloric deficit necessary for weight loss.

Therefore, the key to success is not just eating more frequently, but ensuring that each meal or snack is nutritionally balanced and mindful of portion sizes. Focus on eating whole, unprocessed foods, and be sure to include a good mix of proteins, healthy fats, and fiber-rich carbohydrates in every meal.

eating more frequently

Tips for Losing Weight by Eating More Frequently in Smaller Portions

If you’re interested in trying this approach to weight loss, here are some practical tips to help you get started:

  1. Plan Your Meals and Snacks: Instead of grazing throughout the day, plan your meals and snacks ahead of time. This ensures that you’re not just eating for the sake of eating, but that each meal is nutritionally balanced.
  2. Portion Control is Key: Even though you’re eating more frequently, it’s important not to overeat. Use smaller plates, bowls, or containers to help control your portion sizes and avoid mindless snacking.
  3. Eat Protein-Rich Foods: Protein helps keep you full and satisfied. Include lean proteins like chicken, turkey, tofu, beans, and legumes in each of your meals.
  4. Choose Nutrient-Dense Foods: Prioritize whole foods that are rich in nutrients, like fruits, vegetables, whole grains, and healthy fats. These foods will keep you full longer and provide essential nutrients for your body.
  5. Stay Hydrated: Sometimes, thirst can be mistaken for hunger. Make sure to drink plenty of water throughout the day to stay hydrated and reduce the likelihood of overeating.
  6. Listen to Your Body: Pay attention to your hunger and fullness cues. If you’re not truly hungry, don’t eat just because it’s time for a meal or snack. This will help you avoid eating more calories than necessary.

Final Thoughts

So, can you lose weight by eating more frequently in smaller portions? The answer is: it depends. Eating more frequently can help with portion control, keep your blood sugar stable, and prevent overeating. However, it’s not a magical solution for weight loss. Success ultimately comes down to creating a caloric deficit, eating nutrient-dense foods, and maintaining an overall balanced approach to eating.

If you feel that eating more frequently helps you stay on track with your weight loss goals and improves your relationship with food, it might be worth trying. But remember, there’s no one-size-fits-all solution when it comes to weight loss. Find what works for you and stick with it for the long term. And as always, pair your eating habits with regular exercise for the best results.

In the end, losing weight isn’t about following the latest trend; it’s about adopting a sustainable lifestyle that supports your health and well-being. So go ahead and experiment with eating more frequently, but make sure you’re doing it in a way that benefits your body—and your goals.

Can I Lose Weight by Eating More Frequently in Smaller Portions? Read More »

What Are Healthy Fat Sources for Weight Loss?

When it comes to weight loss, there are many misconceptions that can lead people to make poor choices, especially when it comes to fats. For decades, we’ve been told to cut down on fat in our diets to lose weight, but the truth is that not all fats are created equal. Healthy fat sources for weight loss are an essential part of any balanced diet, helping with everything from metabolism to overall health. But what exactly are these healthy fat sources? How do they help with weight loss? Let’s dive into the world of fats and explore the top healthy fat sources for weight loss.


Understanding Healthy Fats vs. Unhealthy Fats

Before we get into the best fat sources, it’s crucial to understand the difference between healthy and unhealthy fats.

1. Healthy Fats:

Healthy fats are essential for the body and should be included in your diet. These fats help regulate hormones, support brain function, aid in fat-soluble vitamin absorption, and even promote a healthy heart. Healthy fats are primarily unsaturated fats, and they can be found in foods like avocados, olive oil, nuts, seeds, and fatty fish.

2. Unhealthy Fats:

Unhealthy fats, such as trans fats and certain saturated fats, are typically found in processed foods and fried foods. These fats contribute to increased cholesterol levels and can negatively affect your cardiovascular health, so they should be consumed in moderation or avoided altogether.

When we talk about “healthy fat sources for weight loss,” we’re focusing on the fats that can nourish your body and even promote fat loss when consumed in the right amounts. Now, let’s take a look at the best sources of healthy fats.


Top Healthy Fat Sources for Weight Loss

1. Avocados: The King of Healthy Fats

Avocados are often hailed as the ultimate superfood, and for good reason. This creamy fruit is loaded with monounsaturated fats, which are heart-healthy fats known to reduce bad cholesterol levels and lower the risk of heart disease. Not only that, but they’re also rich in fiber, which helps to keep you feeling full longer, preventing overeating.

Why Avocados Are Great for Weight Loss:

  • Monounsaturated Fats: These fats help increase feelings of satiety, which can reduce overall calorie intake.
  • Fiber Content: Fiber slows down digestion, which keeps you feeling fuller for longer.
  • Low in Carbs: Despite being a fruit, avocados are low in carbohydrates, making them perfect for low-carb diets.

How to Use Avocados:

  • Spread on whole-grain toast
  • Add to salads
  • Blend into smoothies
  • Make homemade guacamole
  • Enjoy as a topping for eggs or grilled meats

2. Olive Oil: Liquid Gold for Weight Loss

Olive oil is one of the most popular healthy fats around the globe, especially in Mediterranean diets. It’s primarily made up of monounsaturated fats, which have been linked to a variety of health benefits, including improved cholesterol levels and a lower risk of chronic diseases like type 2 diabetes.

How does Sugar Consumption affect Weight Loss?

Why Olive Oil is Beneficial for Weight Loss:

  • Rich in Antioxidants: Olive oil is packed with antioxidants that fight inflammation and promote healthy metabolic function.
  • Supports Fat Burning: Studies show that olive oil helps activate certain genes that regulate fat metabolism, potentially enhancing fat loss.
  • Easy to Incorporate: Olive oil is incredibly versatile and can be used in dressings, cooking, and even drizzling over vegetables.

How to Use Olive Oil:

  • Drizzle over salads
  • Use for cooking or stir-frying (at moderate heat)
  • Mix into hummus or dips
  • Use in baking recipes

3. Nuts and Seeds: Tiny Powerhouses of Healthy Fats

Nuts and seeds are not only delicious but also packed with healthy fats, fiber, and protein. Almonds, walnuts, chia seeds, and flaxseeds are excellent sources of omega-3 fatty acids and monounsaturated fats, both of which are known to help with fat loss and weight management.

Why Nuts and Seeds Are Effective for Weight Loss:

  • High in Fiber: Fiber helps to control appetite by promoting feelings of fullness.
  • Healthy Fats: These fats boost metabolism and increase the burning of fat.
  • Rich in Protein: Protein contributes to muscle maintenance and repair, keeping your metabolism running efficiently.

How to Use Nuts and Seeds:

  • Snack on a handful of nuts (like almonds, walnuts, or pistachios)
  • Add chia seeds or flaxseeds to smoothies or oatmeal
  • Incorporate them into salads or baked goods
  • Use nut butter as a spread or dip

4. Fatty Fish: Omega-3s for Fat Loss

Fatty fish, such as salmon, mackerel, sardines, and trout, are not just a delicious meal but also a goldmine of omega-3 fatty acids. Omega-3s are a type of polyunsaturated fat that has been shown to reduce inflammation and help with fat metabolism.

Why Fatty Fish Helps with Weight Loss:

  • Boosts Metabolism: Omega-3s have been shown to enhance fat oxidation (the process by which the body burns fat for energy).
  • Reduces Inflammation: Chronic inflammation is often linked to obesity and weight gain. Omega-3s help fight this inflammation, promoting weight loss.
  • Increases Satiety: Fatty fish is rich in protein and healthy fats, both of which help increase feelings of fullness and decrease overall calorie intake.

How to Incorporate Fatty Fish:

  • Grill or bake salmon or mackerel
  • Add sardines to salads or pasta dishes
  • Make homemade fish tacos or wraps
  • Try omega-3-rich fish in soups and stews

5. Coconut Oil: The Tropical Fat

Coconut oil has garnered significant attention for its potential health benefits, particularly when it comes to fat loss. Although coconut oil contains saturated fat, much of it is in the form of medium-chain triglycerides (MCTs), which are metabolized differently from other types of fats. MCTs can increase energy expenditure and promote fat loss.

Why Coconut Oil Is Great for Weight Loss:

  • Boosts Metabolism: MCTs in coconut oil are quickly absorbed and used for energy, rather than being stored as fat.
  • Increases Fat Oxidation: Some studies suggest that coconut oil can help increase fat burning, particularly in the abdominal area.
  • Supports Ketosis: Coconut oil is often used in ketogenic diets, where the body burns fat for energy instead of carbs.

How to Use Coconut Oil:

  • Cook with it at medium heat
  • Add to smoothies or coffee (for a keto-friendly drink)
  • Use in baking recipes
  • Apply to vegetables for roasting

6. Chia Seeds: A Superfood for Healthy Fats

Chia seeds might be small, but they pack a big punch when it comes to healthy fats. These tiny seeds are loaded with omega-3 fatty acids, fiber, and antioxidants, all of which help promote fat loss and reduce inflammation.

Why Chia Seeds Work for Weight Loss:

  • High in Omega-3s: Omega-3s are essential for boosting fat metabolism and supporting overall health.
  • Rich in Fiber: The fiber content in chia seeds helps to increase satiety and curb hunger, reducing overall calorie intake.
  • Water Absorption: Chia seeds can absorb up to 12 times their weight in water, helping you feel full and hydrated longer.

How to Use Chia Seeds:

  • Add to smoothies, oatmeal, or yogurt
  • Use to make chia pudding
  • Sprinkle over salads or fruit bowls
  • Mix into energy bars or baked goods

7. Dark Chocolate: The Sweet Fat Source

Yes, you read that right. Dark chocolate, particularly varieties with 70% or higher cacao, can actually be a healthy fat source when consumed in moderation. Dark chocolate is rich in antioxidants and healthy fats, which can help with weight loss when eaten in controlled portions.

Why Dark Chocolate Can Aid Weight Loss:

  • Rich in Antioxidants: Dark chocolate is loaded with flavonoids that help reduce inflammation and improve metabolic function.
  • Controls Appetite: Dark chocolate can help reduce cravings for sweets, making it easier to stick to a healthy diet.
  • Contains Healthy Fats: Dark chocolate contains monounsaturated fats that support heart health and fat metabolism.

How to Incorporate Dark Chocolate:

  • Snack on a small piece of dark chocolate
  • Melt over fruits or desserts for added flavor
  • Add to smoothies or trail mix
  • Use in baking recipes

Final Verdict: Healthy Fat Sources for Sustainable Weight Loss

Incorporating healthy fat sources for weight loss into your diet is a smart and effective strategy for achieving your weight loss goals. These fats provide essential nutrients that support your overall health, reduce cravings, and keep you feeling full. By adding sources like avocados, olive oil, fatty fish, nuts, and seeds to your meals, you can fuel your body with the right fats that enhance metabolism and fat burning.

Remember, balance is key. Healthy fats should be consumed in moderation, as they are calorie-dense. When combined with a well-rounded diet that includes lean proteins, whole grains, and plenty of fruits and vegetables, healthy fats can help you achieve sustainable weight loss while nourishing your body.

So, next time you’re crafting your meals, don’t be afraid to embrace these healthy fat sources for weight loss. With the right approach, these delicious and nutritious fats can be a powerful tool in your weight loss journey.

What Are Healthy Fat Sources for Weight Loss? Read More »

Are Low Carb Diets Effective for Weight Loss?

In recent years, low-carb diets have gained immense popularity, especially among people looking to shed some extra pounds. The premise is simple: reduce your intake of carbohydrates, and you’ll lose weight. But how true is this statement? Are low-carb diets truly effective for weight loss? In this article, we’ll dive deep into the science, benefits, and potential risks of following a low-carb diet, and ultimately, help you decide if it’s the right approach for your weight loss journey.

What is a Low Carb Diet?

Before we explore whether a low-carb diet is effective for weight loss, it’s essential to understand what it actually is. A low-carb diet focuses on drastically reducing the intake of foods that are rich in carbohydrates, such as bread, pasta, rice, sweets, and sugary beverages. Instead, it emphasizes the consumption of protein-rich foods like lean meats, fish, eggs, and plenty of non-starchy vegetables.

The goal of a low-carb diet is to shift your body from using carbohydrates as its primary source of energy to burning fat for fuel, a metabolic state known as ketosis. When you consume fewer carbs, your body starts to break down fats into ketones, which are then used as an alternative energy source. This is the basis for popular low-carb diets like the Keto Diet, Atkins Diet, and Paleo Diet.

The Science Behind Low Carb Diets and Weight Loss

The science supporting low-carb diets in the context of weight loss is quite compelling. Numerous studies suggest that reducing carbohydrate intake can lead to significant weight loss. Here’s how it works:

  1. Reduced Insulin Levels: Insulin is a hormone that helps regulate blood sugar levels. When you eat carbs, your body breaks them down into glucose (sugar), which triggers an increase in insulin production. Insulin helps store excess glucose in fat cells. A low-carb diet reduces insulin levels, which means less glucose is stored as fat, making it easier for the body to burn fat for energy.
  2. Increased Fat Burning: By cutting carbs, the body enters a state of ketosis, where it burns fat for fuel. This process leads to faster weight loss, particularly from stored fat.
  3. Appetite Suppression: Many individuals report feeling less hungry on a low-carb diet. This could be because fat and protein take longer to digest than carbohydrates, leading to greater feelings of fullness. Moreover, ketones produced in ketosis may have appetite-suppressing effects.
  4. Water Weight Loss: One of the initial effects of a low-carb diet is the loss of water weight. Carbohydrates are stored in the body along with water. For every gram of glycogen (carbohydrate storage), there’s approximately 3 grams of water. When you reduce carbs, your body uses up glycogen and sheds excess water, leading to rapid but temporary weight loss.
  5. Improved Fat Metabolism: A low-carb diet can help improve fat oxidation (fat-burning) during both rest and exercise. Studies have shown that when carbohydrate intake is reduced, the body becomes more efficient at using fat as a source of energy.

Low Carb Diets vs. Other Diets

Low-carb diets are often compared to other popular weight loss plans, like low-fat diets and calorie-restricted diets. So, how do low-carb diets stack up against these approaches?

  • Low-Carb Diet vs. Low-Fat Diet: While both low-carb and low-fat diets restrict certain macronutrients, the key difference is the emphasis on protein and fats in low-carb diets. Studies have shown that low-carb diets may be more effective for weight loss than low-fat diets. One reason for this is that low-carb diets often lead to greater satiety, reducing overall calorie intake.
  • Low-Carb Diet vs. Calorie Restriction: When you simply restrict calories, the focus is on reducing the total energy you consume. A low-carb diet naturally leads to a reduction in calorie intake because of the appetite-suppressing effects of ketones. Additionally, low-carb diets don’t require meticulous calorie counting, which can be exhausting and difficult to maintain long-term.
  • Low-Carb Diet vs. Mediterranean Diet: The Mediterranean diet, which emphasizes healthy fats, whole grains, and plenty of fruits and vegetables, is another popular approach to weight loss. While both diets can promote weight loss, low-carb diets tend to lead to faster results, especially in the initial stages.

The Benefits of a Low Carb Diet

When done correctly, a low-carb diet can offer numerous benefits beyond just weight loss. Here are some of the key benefits:

  1. Improved Blood Sugar Control: Low-carb diets have been shown to improve blood sugar levels, especially for people with type 2 diabetes or those at risk. By reducing carbohydrate intake, the body doesn’t need to produce as much insulin, helping to stabilize blood sugar.
  2. Enhanced Heart Health: Studies indicate that low-carb diets can improve heart health by lowering triglyceride levels, reducing LDL (bad) cholesterol, and raising HDL (good) cholesterol. These changes can reduce the risk of cardiovascular diseases, like heart attacks and strokes.
  3. Better Mental Clarity: Many people on low-carb diets report clearer thinking and better mental focus. This may be due to the brain’s reliance on ketones for energy, which is considered a more stable and efficient fuel source than glucose.
  4. Reduced Inflammation: A low-carb diet can lower inflammation in the body, which is linked to various chronic diseases. Reduced inflammation can help prevent conditions like arthritis, heart disease, and even cancer.
  5. Increased Physical Endurance: While carbohydrates are often used by athletes for quick bursts of energy, fat is the primary fuel source for long-lasting endurance. By switching to fat as your body’s main fuel source, you may experience improved stamina during long workouts.

The Risks and Potential Downsides of a Low Carb Diet

Although a low-carb diet can offer numerous benefits, it’s not without its risks. Here are some potential downsides to be aware of:

  1. Nutrient Deficiency: Carbohydrates are a vital source of fiber, vitamins, and minerals. A strict low-carb diet may lead to nutrient deficiencies, especially if it excludes healthy fruits, vegetables, and whole grains. It’s important to focus on nutrient-dense, low-carb foods like leafy greens and non-starchy vegetables to avoid deficiencies.
  2. Keto Flu: When first starting a low-carb diet, especially the more extreme versions like the ketogenic diet, some individuals may experience what’s known as the “keto flu.” Symptoms include fatigue, headaches, dizziness, irritability, and nausea. These symptoms are usually temporary but can make the transition to a low-carb lifestyle difficult for some people.
  3. Difficulty Maintaining the Diet Long-Term: While a low-carb diet may work for short-term weight loss, many people find it challenging to stick to in the long run. Carbs are a primary part of many people’s diets, and cutting them out can feel restrictive, leading to eventual cravings and overeating.
  4. Kidney and Liver Strain: The increased breakdown of proteins and fats on a low-carb diet may put additional strain on the kidneys and liver. Individuals with preexisting kidney or liver conditions should consult a doctor before starting such a diet.
  5. Potential for Increased Cholesterol Levels: Some individuals on low-carb diets, especially those with high levels of saturated fat, may experience an increase in cholesterol levels. It’s crucial to focus on healthy fats (like avocados, olive oil, and nuts) rather than unhealthy fats to mitigate this risk.

How to Make a Low Carb Diet Work for You

If you’re interested in trying a low-carb diet for weight loss, here are some tips to ensure success:

  1. Focus on Whole Foods: Rather than relying on processed, low-carb snacks, aim to include whole, nutrient-dense foods in your diet, such as lean proteins, non-starchy vegetables, and healthy fats.
  2. Stay Hydrated: Drinking plenty of water is essential, especially in the early stages of a low-carb diet. Dehydration is common as your body sheds excess water from the initial weight loss.
  3. Plan Your Meals: Meal planning is key to staying on track with a low-carb diet. Without proper planning, you might find yourself reaching for carb-heavy options when you get hungry.
  4. Exercise Regularly: Regular physical activity can enhance the effects of a low-carb diet by accelerating fat loss and improving overall health. Aim for a combination of strength training and cardiovascular exercise.
  5. Consult a Healthcare Professional: Before making any significant dietary changes, especially if you have any underlying health conditions, consult a doctor or nutritionist. They can help you create a plan that’s right for you.

Final Verdict

Low-carb diets can be an effective and sustainable approach to weight loss for many people. They help regulate insulin levels, increase fat burning, and promote feelings of fullness, which can all contribute to weight loss. However, they are not without their challenges. Nutrient deficiencies, the risk of muscle loss, and difficulty maintaining the diet long-term can pose issues.

If you’re considering a low-carb diet, take the time to understand how it works, plan your meals carefully, and make sure you’re getting all the essential nutrients your body needs. For some, it might be the perfect solution for shedding those extra pounds, but for others, a different approach may be more suitable.

Ultimately, the best weight loss plan is the one that aligns with your lifestyle, preferences, and long-term goals. Whether it’s a low-carb diet, a balanced approach, or another method, consistency and sustainability are key.

Are Low Carb Diets Effective for Weight Loss? Read More »

Who Sponsors Clinical Trials?

Clinical trials are the backbone of medical advancements, bringing new drugs, devices, and therapies to the market. These meticulously designed studies test the safety and efficacy of medical interventions, paving the way for improved healthcare outcomes. But who foots the bill for these complex and often expensive endeavors? Understanding who sponsors clinical trials provides insight into the intricate ecosystem of medical research and the motivations driving innovation. In this article, we’ll dive deep into the world of clinical trial sponsorship, exploring the key players, their roles, and the impact of their contributions.


What Are Clinical Trials?

Before we explore the sponsors, let’s briefly define what a clinical trial entails. A clinical trial is a research study conducted with human volunteers to evaluate the effects of a medical intervention, such as a new drug, medical device, vaccine, or treatment protocol. These trials are conducted in phases, each with a specific purpose:


Phase I: Tests safety and dosage in a small group.
Phase II: Evaluates efficacy and side effects in a larger group.
Phase III: Confirms effectiveness, monitors side effects, and compares the intervention to existing treatments in large populations.
Phase IV: Post-market studies to gather additional information on long-term effects.

Clinical trials are resource-intensive, requiring significant financial investment, expertise, and time. The costs can range from hundreds of thousands to billions of dollars, depending on the trial’s scope, duration, and complexity. This brings us to the critical question: who sponsors clinical trials, and why?


The Key Sponsors of Clinical Trials

Clinical trials are funded by a variety of entities, each with distinct motivations and goals. The primary sponsors include pharmaceutical and biotechnology companies, government agencies, academic institutions, nonprofit organizations, and, in some cases, individual philanthropists or crowdsourcing efforts. Let’s break down each category.


1. Pharmaceutical and Biotechnology Companies

The pharmaceutical and biotechnology industries are the largest sponsors of clinical trials worldwide. These companies invest heavily in research and development (R&D) to bring new drugs, biologics, and medical devices to market. According to the Pharmaceutical Research and Manufacturers of America (PhRMA), the biopharmaceutical industry spent over $100 billion on R&D in the United States alone in 2022, with a significant portion allocated to clinical trials.


Why Do They Sponsor Clinical Trials?

Profit Motive: Developing a successful drug or device can generate substantial revenue. For example, blockbuster drugs like Humira or Keytruda have earned billions for their manufacturers.
Regulatory Requirements: To gain approval from regulatory bodies like the U.S. Food and Drug Administration (FDA) or the European Medicines Agency (EMA), companies must provide robust clinical trial data demonstrating safety and efficacy.
Market Expansion: Clinical trials allow companies to explore new indications for existing drugs, expanding their market potential.


Challenges and Criticisms

While pharmaceutical companies drive innovation, their sponsorship comes with scrutiny. Critics argue that profit-driven motives may lead to biased trial designs, selective reporting of results, or prioritization of lucrative markets over unmet medical needs. To address these concerns, regulatory agencies enforce strict guidelines, and independent oversight bodies, such as Institutional Review Boards (IRBs), monitor trial conduct.

2. Government Agencies

Government agencies play a significant role in sponsoring clinical trials, particularly for research that may not attract commercial interest. In the United States, the National Institutes of Health (NIH) is a leading sponsor, funding thousands of clinical trials annually. Other agencies, such as the Centers for Disease Control and Prevention (CDC) and the Department of Defense (DoD), also contribute.


Why Do Governments Sponsor Clinical Trials?

Public Health Priorities: Governments fund trials for diseases with significant public health impacts, such as cancer, infectious diseases, or rare disorders.
Noncommercial Research: They support studies that may not be profitable for private companies, such as trials for neglected tropical diseases or preventive interventions.
Emergency Response: During public health crises, like the COVID-19 pandemic, government agencies rapidly mobilize funding for clinical trials to develop vaccines and treatments.

Examples of Government-Sponsored Trials

What Are Clinical Trials and Why Are They Important?


The NIH’s ClinicalTrials.gov database lists thousands of trials funded by federal agencies, covering areas like Alzheimer’s disease, HIV/AIDS, and mental health.
Operation Warp Speed, a U.S. government initiative, provided billions of dollars to accelerate COVID-19 vaccine trials, collaborating with private companies like Pfizer and Moderna.


Advantages and Limitations

Government-funded trials are often seen as impartial, prioritizing patient outcomes over profits. However, their budgets are subject to political and economic fluctuations, which can limit their scope compared to industry-funded trials.


3. Academic and Research Institutions

Universities, medical schools, and research hospitals frequently sponsor clinical trials, often in collaboration with other entities. These institutions are hubs of scientific discovery, conducting trials to advance medical knowledge and improve patient care.
Why Do Academic Institutions Sponsor Clinical Trials?

Scientific Discovery: Academic researchers aim to answer fundamental questions about disease mechanisms, treatment efficacy, or preventive strategies.
Training and Education: Clinical trials provide hands-on experience for medical students, researchers, and clinicians.
Collaboration: Academic institutions often partner with industry or government sponsors, leveraging their expertise and infrastructure.

Funding Sources

Academic institutions typically rely on grants from government agencies, nonprofit organizations, or industry partners. For example, the NIH’s National Cancer Institute funds numerous cancer-related trials conducted at academic medical centers.

Impact of Academic Sponsorship

Academic-sponsored trials often focus on innovative or exploratory research, such as novel therapies for rare diseases or personalized medicine approaches. They also contribute to the training of future scientists and clinicians, ensuring a steady pipeline of expertise in clinical research.

4. Nonprofit Organizations and Foundations

Nonprofit organizations and charitable foundations are vital sponsors of clinical trials, particularly for diseases that receive limited attention from industry or government. Examples include the Bill & Melinda Gates Foundation, the American Cancer Society, and disease-specific groups like the Cystic Fibrosis Foundation.


Why Do Nonprofits Sponsor Clinical Trials?

Mission-Driven Goals: Nonprofits focus on addressing unmet medical needs, such as rare diseases, pediatric conditions, or global health challenges.
Patient Advocacy: Many organizations are founded by patients or their families, driving research to find cures or improve quality of life.
Bridging Gaps: Nonprofits often fund early-stage research or trials that bridge the gap between academic discovery and industry development.


Notable Examples

The Cystic Fibrosis Foundation invested heavily in clinical trials for drugs like Trikafta, transforming the lives of patients with cystic fibrosis.
The Michael J. Fox Foundation funds trials to develop treatments for Parkinson’s disease, including studies on disease-modifying therapies.


Benefits and Challenges

Nonprofit-sponsored trials are highly focused and patient-centered, but their funding is often limited compared to industry or government resources. They may rely on donations, grants, or partnerships to sustain their efforts.

5. Individual Philanthropists and Crowdsourcing

In rare cases, clinical trials are funded by individual philanthropists or crowdsourcing campaigns. Wealthy individuals may donate to specific causes, while grassroots efforts leverage online platforms to raise funds.
Examples

Philanthropy: High-profile donors like Michael Bloomberg have supported clinical research in areas like public health and cancer.
Crowdsourcing: Platforms like GoFundMe have been used to fund small-scale trials or experimental treatments, particularly for rare diseases.


Opportunities and Risks

While these funding sources democratize research, they often lack the scale and rigor of institutional sponsors. Crowdsourced trials may also face ethical concerns, such as inadequate oversight or unrealistic expectations.


Collaborative Sponsorship Models

In many cases, clinical trials are sponsored by a combination of entities working together. For example:

Public-Private Partnerships: Government agencies and pharmaceutical companies collaborate to share costs and expertise, as seen in COVID-19 vaccine development.
Consortia: Multiple stakeholders, including industry, academia, and nonprofits, pool resources to tackle complex diseases like Alzheimer’s or cancer.
Contract Research Organizations (CROs): While not sponsors themselves, CROs are hired by sponsors to manage trial operations, ensuring efficiency and compliance.

These collaborative models maximize resources, reduce duplication, and accelerate the pace of research.


The Role of Patients and Volunteers

While not sponsors in the financial sense, patients and volunteers are essential to clinical trials. Their participation is invaluable, and sponsors often cover costs like travel, medical care, or stipends to ensure accessibility. Patient advocacy groups also influence trial design and funding priorities, ensuring that research aligns with real-world needs.
The Economics of Clinical Trial Sponsorship
The cost of conducting a clinical trial varies widely based on factors like:


Phase: Phase III trials are the most expensive due to large sample sizes and long durations.
Therapeutic Area: Oncology and neurology trials are among the costliest due to complex endpoints and regulatory requirements.
Geography: Trials conducted in multiple countries face higher logistical costs.

According to a 2020 study published in JAMA Internal Medicine, the median cost of a clinical trial is approximately $19 million, with some trials exceeding $1 billion. Sponsors must balance these costs against potential benefits, whether financial, scientific, or societal.


Transparency and Ethical Considerations

Sponsorship comes with responsibilities. All sponsors must adhere to ethical standards, ensuring participant safety, informed consent, and data integrity. Transparency is critical, particularly for industry-sponsored trials, where conflicts of interest may arise. Initiatives like ClinicalTrials.gov and the World Health Organization’s International Clinical Trials Registry Platform promote public access to trial information, fostering trust.


The Future of Clinical Trial Sponsorship

The landscape of clinical trial sponsorship is evolving, driven by technological advancements and global health challenges. Key trends include:

Decentralized Trials: Digital tools and remote monitoring reduce costs, potentially attracting new sponsors.
Precision Medicine: Trials targeting specific genetic profiles require innovative funding models.
Global Collaboration: International partnerships address pandemics and neglected diseases, pooling resources across borders.

Emerging sponsors, such as tech companies (e.g., Google’s Verily) and patient-driven initiatives, are also entering the space, diversifying the funding ecosystem.

Clinical trials are a cornerstone of medical progress, and their sponsors play a pivotal role in shaping the future of healthcare. From pharmaceutical giants to government agencies, academic institutions to nonprofits, and even individual donors, each sponsor brings unique motivations and resources to the table. Understanding who sponsors clinical trials reveals the complex interplay of science, economics, and ethics that drives innovation. As the field evolves, collaborative and innovative sponsorship models will continue to accelerate the development of life-saving treatments, benefiting patients worldwide.

By shedding light on the funding behind clinical trials, we gain a deeper appreciation for the collective effort required to turn scientific discoveries into tangible solutions. Whether you’re a patient, researcher, or simply curious, recognizing the diverse sponsors of clinical trials underscores the shared commitment to advancing human health.

Who Sponsors Clinical Trials? Read More »

What Are Clinical Trials and Why Are They Important?

Clinical trials are a cornerstone of modern medicine, playing a pivotal role in advancing healthcare and improving lives. These carefully designed research studies evaluate the safety and effectiveness of new medical treatments, drugs, devices, or interventions. By systematically testing these innovations on human volunteers, clinical trials provide the evidence needed to bring groundbreaking therapies to the public. But what exactly are clinical trials, and why do they matter so much? In this comprehensive guide, we’ll explore the ins and outs of clinical trials, their significance in medical progress, and how they impact patients and society.


Understanding Clinical Trials: The Basics

At their core, clinical trials are scientific studies conducted to assess whether a new medical intervention—such as a drug, vaccine, medical device, or treatment protocol—is safe, effective, and beneficial for patients. These trials are meticulously planned and follow strict ethical and scientific guidelines to ensure participant safety and reliable results.
Clinical trials typically involve human volunteers who agree to participate in the study under controlled conditions. Researchers collect data on how the intervention performs, monitoring factors like efficacy, side effects, and overall impact on health. The findings from these studies help determine whether a treatment should be approved for widespread use, modified, or abandoned.
The process of conducting clinical trials is rigorous and often spans several years. It involves collaboration among scientists, doctors, regulatory bodies, and participants. Trials are usually conducted in phases, each with a specific purpose, to gradually build evidence about the intervention’s safety and effectiveness.


The Phases of Clinical Trials

Clinical trials are divided into distinct phases, each serving a unique role in the research process. Here’s a breakdown of the four main phases:

Phase I: Safety Testing

Purpose: Phase I trials focus on evaluating the safety of a new intervention in a small group of healthy volunteers (typically 20-100 participants).
Goals: Researchers determine safe dosage ranges, identify side effects, and assess how the body processes the treatment.
Duration: This phase is short, often lasting a few months.
Example: A new cancer drug might be tested to see if it causes adverse reactions at different doses.

Phase II: Efficacy and Side Effects

Purpose: Phase II trials involve a larger group (100-300 participants) and aim to assess the intervention’s effectiveness while continuing to monitor safety.
Goals: Researchers gather preliminary data on whether the treatment works for a specific condition and refine dosage recommendations.
Duration: This phase can last several months to two years.
Example: The same cancer drug might be tested on patients with a specific type of cancer to see if it shrinks tumors.

Phase III: Large-Scale Testing

Purpose: Phase III trials are conducted on a much larger scale (1,000-3,000 participants) to confirm the intervention’s effectiveness, monitor side effects, and compare it to existing treatments or a placebo.
Goals: These trials provide comprehensive data to support regulatory approval.
Duration: This phase can last several years.
Example: The cancer drug is now tested across multiple hospitals to compare its effectiveness against standard treatments.

Phase IV: Post-Market Surveillance

Purpose: Phase IV trials occur after a treatment has been approved and is available to the public. They monitor long-term safety and effectiveness in a broader population.
Goals: Researchers identify rare side effects, assess long-term benefits, and explore additional uses.
Duration: This phase can continue for many years.
Example: The cancer drug is monitored to ensure it remains safe and effective as more patients use it.

Each phase builds on the previous one, ensuring that only safe and effective interventions reach the market. This structured approach is why clinical trials are so critical to medical innovation.


Why Are Clinical Trials Important?

Clinical trials are the backbone of medical advancements, driving progress in healthcare and improving patient outcomes. Here are some key reasons why clinical trials are essential:

1. Advancing Medical Knowledge

Clinical trials generate critical data that expands our understanding of diseases and how to treat them. They provide evidence-based insights into what works, what doesn’t, and why. This knowledge shapes medical guidelines, informs clinical practice, and fuels further research.
For example, clinical trials have been instrumental in developing life-saving treatments for conditions like cancer, HIV/AIDS, and heart disease. Without these trials, doctors would rely on guesswork or anecdotal evidence, which could lead to ineffective or harmful treatments.

2. Ensuring Safety and Efficacy

Before any new drug or medical device can be approved for public use, it must undergo rigorous testing through clinical trials. Regulatory agencies like the U.S. Food and Drug Administration (FDA) and the European Medicines Agency (EMA) rely on trial data to evaluate whether a treatment is safe and effective.
Clinical trials help identify potential risks, such as side effects or adverse reactions, ensuring that only treatments with a favorable risk-benefit profile reach patients. This process protects public health and builds trust in medical interventions.

3. Improving Patient Care

The ultimate goal of clinical trials is to improve patient care. By identifying better treatments, clinical trials enhance the quality of life for individuals with chronic or life-threatening conditions. They also contribute to personalized medicine, where treatments are tailored to specific patient groups based on genetic, environmental, or lifestyle factors.
For instance, clinical trials have led to targeted therapies for breast cancer patients with specific genetic mutations, offering more effective and less toxic options than traditional chemotherapy.

4. Providing Access to Cutting-Edge Treatments

Participating in clinical trials gives patients access to new treatments that are not yet available to the public. For individuals with serious or rare conditions, this can be a lifeline, offering hope when standard treatments have failed.
In addition to receiving innovative therapies, trial participants often benefit from close medical monitoring and care from specialized research teams. This can lead to better health outcomes, even for those receiving a placebo.

5. Addressing Unmet Medical Needs

Clinical trials play a crucial role in addressing gaps in healthcare, particularly for rare diseases or conditions with limited treatment options. They drive the development of therapies for underserved populations, ensuring that everyone has access to effective care.
For example, clinical trials have led to breakthroughs in treatments for rare genetic disorders like cystic fibrosis, which previously had few viablea significant portion of the population. These advancements would not have been possible without the structured research provided by clinical trials.

6. Shaping Public Health Policies

The data from clinical trials informs public health policies and guidelines. For instance, clinical trials on vaccines have guided global immunization programs, saving millions of lives. Similarly, trials on lifestyle interventions, such as smoking cessation or dietary changes, have shaped public health campaigns to prevent chronic diseases.


How Do Clinical Trials Work?

Clinical trials are complex, involving multiple stakeholders, including researchers, participants, sponsors, and regulatory bodies. Here’s a closer look at how they operate:

1. Study Design

Every clinical trial begins with a detailed study protocol, which outlines the trial’s objectives, methodology, participant criteria, and data collection methods. The protocol ensures consistency and minimizes bias. Common study designs include:

Randomized Controlled Trials (RCTs): Participants are randomly assigned to receive the intervention or a control (e.g., placebo or standard treatment).
Double-Blind Trials: Neither the participants nor the researchers know who is receiving the intervention or placebo, reducing bias.
Crossover Trials: Participants receive both the intervention and control at different times, allowing researchers to compare outcomes within the same group.

2. Participant Recruitment

Recruiting participants is a critical step in clinical trials. Researchers seek volunteers who meet specific eligibility criteria, such as age, medical history, or disease stage. Diversity in trial participants is essential to ensure that findings apply to a broad population.
Participants may be recruited through healthcare providers, online platforms, or community outreach. Informed consent is a key ethical requirement, ensuring that participants understand the trial’s purpose, risks, and benefits before enrolling.

3. Data Collection and Analysis

During the trial, researchers collect data on various outcomes, such as symptom improvement, side effects, or disease progression. Advanced statistical methods are used to analyze the data and determine whether the intervention is effective and safe.

4. Regulatory Oversight

Clinical trials are subject to strict oversight by regulatory bodies and ethics committees. These organizations review study protocols, monitor participant safety, and ensure compliance with ethical standards. In the U.S., the FDA oversees clinical trials, while Institutional Review Boards (IRBs) provide ethical guidance at the institutional level.
Who Can Participate in Clinical Trials?

Clinical trials rely on volunteers, and eligibility varies depending on the study’s goals. Some trials seek healthy individuals, while others focus on patients with specific conditions. Factors like age, gender, medical history, and current health status may influence eligibility.
If you’re interested in participating in a clinical trial, talk to your healthcare provider or visit websites like ClinicalTrials.gov, which lists ongoing trials worldwide. Before joining, carefully review the study’s requirements, risks, and benefits to make an informed decision.


Challenges in Clinical Trials

While clinical trials are essential, they face several challenges:

Recruitment Difficulties: Finding enough eligible participants, especially for rare diseases, can be time-consuming.
Diversity Issues: Historically, clinical trials have underrepresented certain groups, such as women, minorities, and older adults, limiting the generalizability of findings.
Cost and Time: Clinical trials are expensive and can take years to complete, delaying the availability of new treatments.
Ethical Concerns: Balancing participant safety with the need for scientific progress requires careful ethical considerations.

Researchers are addressing these challenges through innovative approaches, such as virtual trials, adaptive study designs, and efforts to increase diversity in participant recruitment.


The Future of Clinical Trials

The landscape of clinical trials is evolving rapidly, driven by technological advancements and changing healthcare needs. Some exciting trends include:

Digital and Virtual Trials: Wearable devices, mobile apps, and telemedicine are making it easier to conduct trials remotely, improving accessibility and convenience.
Artificial Intelligence (AI): AI is being used to analyze trial data, predict outcomes, and identify suitable participants.
Precision Medicine: Clinical trials are increasingly focused on personalized treatments tailored to individual genetic profiles.
Global Collaboration: International partnerships are accelerating the development of treatments for global health challenges, such as infectious diseases.

These innovations promise to make clinical trials more efficient, inclusive, and impactful in the years to come.

Clinical trials are a vital engine of medical progress, transforming scientific discoveries into real-world treatments that save lives and improve health. By rigorously testing new interventions, clinical trials ensure that patients receive safe, effective, and evidence-based care. They offer hope to those with untreatable conditions, drive innovation, and shape the future of healthcare.
Whether you’re a patient, a healthcare provider, or simply curious about medical research, understanding the importance of clinical trials empowers you to support and engage with this critical process. From developing life-saving drugs to shaping public health policies, clinical trials are at the heart of a healthier, brighter future.
If you’re inspired to learn more or participate in a clinical trial, resources like ClinicalTrials.gov or your healthcare provider can guide you. Together, we can continue to advance medical science and improve lives through the power of clinical trials.

What Are Clinical Trials and Why Are They Important? Read More »

Astell SVS1400: The Ultimate 1400 L Industrial Autoclave Solution

The Astell SVS1400 autoclave represents the pinnacle of large-capacity sterilization technology, offering an impressive 1400 litre chamber within Astell’s renowned SQUARE MAX range. Designed for high-throughput environments where reliability and versatility are paramount, this model combines sophisticated engineering with user-friendly operation. With customizable features, advanced safety mechanisms, and options for both steam generator and direct steam configurations, the SVS1400 provides an efficient solution for facilities requiring industrial-scale sterilization capabilities while maintaining Astell’s century-plus reputation for excellence in sterilization technology.


Understanding the SQUARE MAX Range and the SVS1400 Model

The SVS1400 sits at the top end of Astell’s SQUARE MAX autoclave range, which features five different chamber sizes from 600 to 1400 litres. As the largest model in this premium lineup, the SVS1400 is specifically engineered for facilities with substantial sterilization requirements. Astell Scientific, a company with a heritage dating back to 1884, has developed this range to address the needs of industries requiring high-volume, reliable sterilization solutions.

The SQUARE MAX range, including the SVS1400 model, is highly customizable and capable of sterilizing almost anything, depending on the configuration selected. This versatility makes it an ideal choice for research institutions, pharmaceutical manufacturers, and industrial facilities where diverse sterilization requirements are common.


Technical Specifications and Performance Features

The SVS1400 boasts impressive dimensions and capabilities that set it apart in the industrial autoclave market. With a spacious chamber measuring 700 x 1000 x 2000 mm (W x H x D), the unit offers ample space for bulky or numerous items while maintaining a relatively compact overall footprint of 2000 x 2000 x 2500 mm. This efficient use of space makes it suitable even for facilities where floor area is at a premium.

Power options are equally impressive, with the standard configuration featuring a robust 72kW steam generator, though a direct steam version operating at 4kW is also available at no extra cost. This flexibility allows facilities to choose the most appropriate setup based on their existing infrastructure and specific requirements. The unit can be configured with either single or double doors, making it adaptable for pass-through installations where clean and dirty sides need to be separated.

Central to the user experience is Astell’s intuitive 5.7″ colour touchscreen controller, which provides straightforward operation despite the industrial scale of the equipment. This modern interface allows operators to monitor cycle progress, access stored programs, and review sterilization data with ease.


Advanced Options for Enhanced Performance

What truly distinguishes the SVS1400 is its adaptability through various advanced options. For facilities dealing with porous loads or wrapped instruments where air pockets could compromise sterilization, the AVC001 advanced pulsar vacuum option provides superior air removal. When used in conjunction with the integral steam generator and a heated jacket, this system enables effective drying of all load types, significantly enhancing versatility.

The external jacket option adds another dimension to the SVS1400’s capabilities. This feature effectively creates an additional layer around the autoclave chamber that can be independently heated to enhance drying or flooded with water to accelerate cooling. This dual functionality contributes to faster cycle times and improved throughput, potentially increasing operational efficiency.

For applications requiring precise documentation and validation, the SVS1400 can be equipped with FDA 21 CFR part 11 compliant software, making it suitable for regulated industries such as pharmaceuticals. Calibration and validation services are also available, ensuring ongoing compliance with relevant standards and regulations.


Safety Features and Built-in Protections

Safety remains paramount in Astell’s design philosophy, and the SVS1400 incorporates multiple protective measures. Standard safety features include over-temperature protection, a cooling lock to prevent door opening at unsafe temperatures, a safety valve test program, and an accessible emergency stop button.

The door mechanism incorporates sophisticated safety interlocks that prevent cycle initiation unless the door is properly closed and sealed. Similarly, the system prohibits door opening until chamber pressure and temperature have reached safe levels. These automated protections minimize operator risk when working with such a large-capacity, high-pressure system.

The SVS1400’s doors are thermally insulated to prevent surface temperatures from presenting hazards to operators, while the door seal is designed to resist both steam and vacuum without trapping foreign materials. These thoughtful safety features reflect Astell’s long experience in autoclave manufacturing and commitment to operator wellbeing.


Real-World Applications and Versatility

The SVS1400’s substantial capacity makes it particularly valuable for high-throughput environments or facilities dealing with bulky and awkward loads. In pharmaceutical manufacturing, for instance, the autoclave can efficiently sterilize large batches of media, equipment, or waste materials, maintaining production schedules while ensuring sterility.

Research institutions with substantial material processing requirements benefit from the SVS1400’s ability to handle diverse load types. As Garth Barnard, Managing Director at Cantor + Nissel notes about Astell autoclaves generally, “Rapid cycle times are important, but so is flexibility. The latest version of Astell’s software allows us to create our own cycle parameters so that we can run different cycles depending on the products being sterilised.”

Industrial facilities processing raw materials or finished products in large volumes can leverage the SVS1400’s robust construction and consistent performance to maintain production quality with minimal downtime. The availability of customization options means the autoclave can be tailored to specific process requirements, enhancing its value as a long-term investment.


Customer Support and Service Excellence

Beyond the technical specifications, Astell’s reputation for customer service adds significant value to the SVS1400 offering. As Steve Guy, M&E Facility Manager at John Innes Centre, observes, “Astell are always quick to respond, and it’s usually the same service engineers – which helps as some of our equipment is quite unique… Their customer service has always been good so, when an autoclave reaches the end of its life, we generally replace it with an Astell unit.”

This consistent support is particularly important for facilities where autoclave downtime can significantly impact operations. The availability of trained technicians familiar with the specific model contributes to faster resolution of any issues and minimizes operational disruptions.


A Premium Solution for Industrial Sterilization Needs

The Astell SVS1400 represents a premium solution for large-capacity sterilization requirements, combining impressive 1400 litre capacity with flexible configuration options and modern control systems. Its robust construction, comprehensive safety features, and adaptability to various sterilization protocols make it suitable for demanding applications across multiple industries.

For facilities requiring industrial-scale sterilization capabilities, the SVS1400 delivers the perfect balance of capacity, reliability, and technological sophistication. Backed by Astell’s century-plus heritage in sterilization excellence and commitment to customer support, this autoclave represents not just a piece of equipment, but a long-term sterilization solution designed to meet evolving needs across its operational lifespan.

Whether upgrading an existing facility or equipping a new installation, the SVS1400 offers the capacity, features, and support to ensure reliable, efficient sterilization for years to come. As the largest model in Astell’s respected SQUARE MAX range, it embodies the culmination of generations of sterilization expertise in a modern, high-performance package.

Astell SVS1400: The Ultimate 1400 L Industrial Autoclave Solution Read More »